Conditions & surgery · should I…?
Should you have arthroscopic surgery?
Arthroscopic knee or shoulder surgery, or physical therapy first? A physical therapist walks through what the research shows, through one patient’s decision.
Licensed orthopedic physical therapist, 30 years of clinical experience. Former clinic owner and
author of Pain Patterns, winner of the 2025 NIEA Award, and creator of a systems-based
approach to chronic pain used in his APTA-approved continuing education course.
Right now I’m working with a massage therapist who tore the meniscus in his knee. He’s very active, and when he came to me, he’d spent six months doing everything right: resting it, following my recommendations and those of another physical therapist, and reading up on his own. The pain hadn’t gone away. He was going a little crazy. He couldn’t do the things he loves, and surgery was starting to look like an attractive solution.
I’m in a similar boat myself. A few weeks ago I slipped on a wet rock while trail running and twisted my knee. Since then I’ve had pain in one spot, right on the inner joint line, which I’m assuming means a meniscus tear to some degree. I haven’t had an MRI.
At first blush, this looks simple. He has a meniscus tear. A surgeon trims off the torn piece, and the problem is solved.
Not so fast.
Arthroscopic surgery is one of the most common orthopedic operations there is. But some of the best studies we have randomly assigned patients to real surgery or a fake one, and nobody could tell the difference in how people recovered.1, 2
I’m not going to tell him, or you, whether to have surgery. What I can do is lay out what the research shows, so your decision gets made with the whole picture in mind.
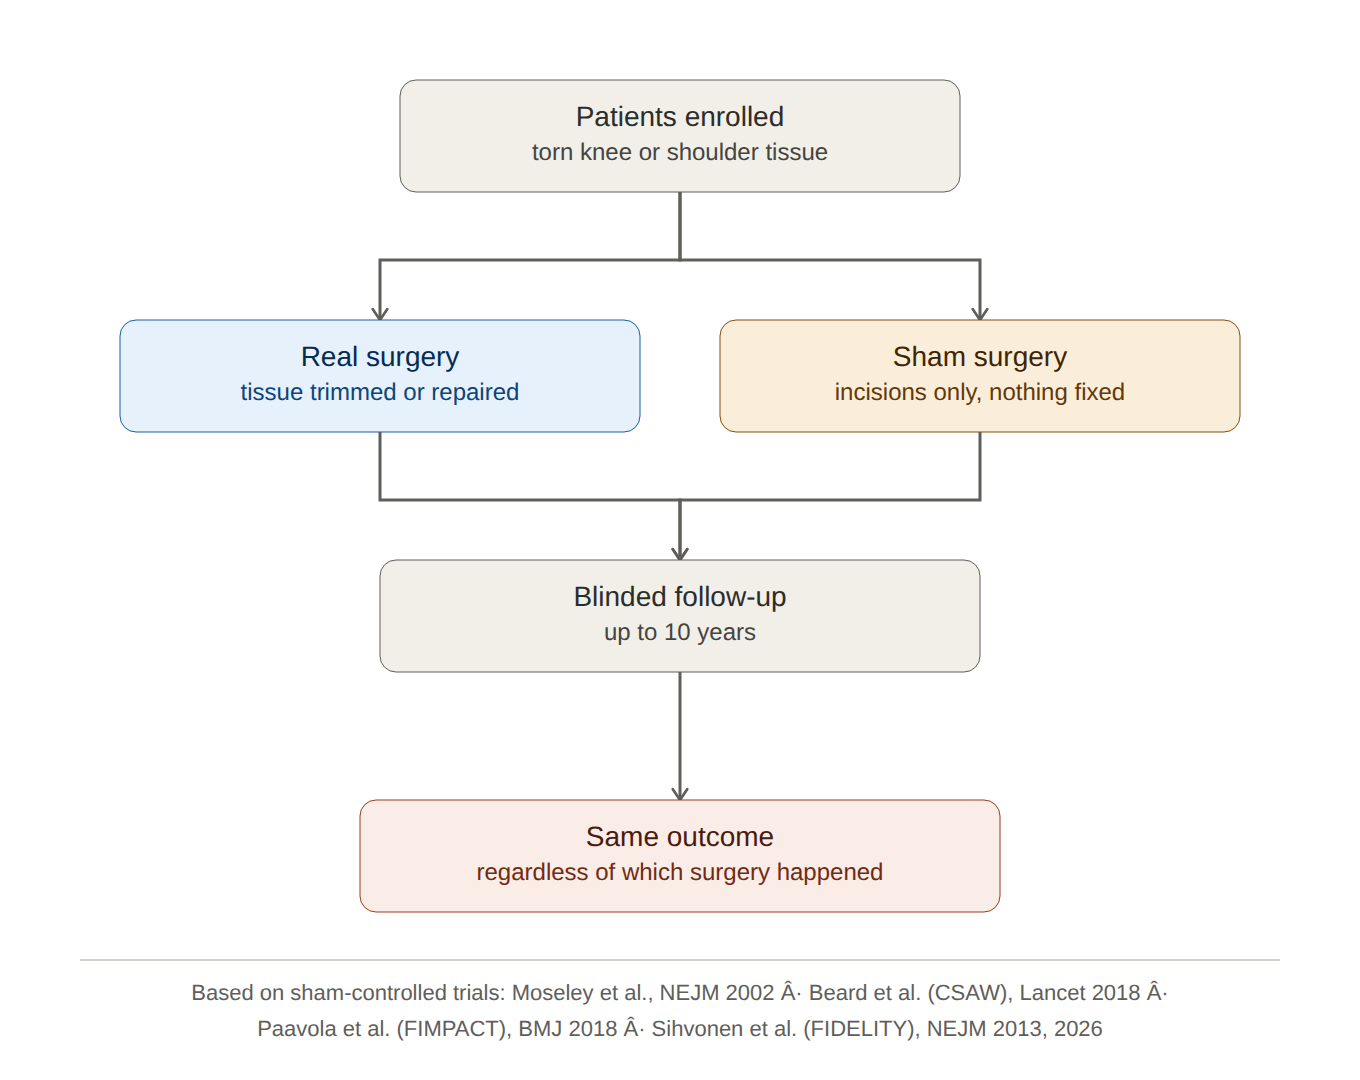
This article is about how to think through a decision, not a recommendation for or against surgery in your case. Only you and your surgeon can make that call, with your imaging, your history, and your goals in front of you.
The short answer, based on the research
- Degenerative knee problems (wear-and-tear meniscus tears and knee arthritis): multiple studies, including some that compared real surgery with fake surgery, found no meaningful difference between surgery and not having it.1
- Shoulder impingement pain (pain lifting the arm, without a full-thickness rotator cuff tear): the same pattern. Real surgery did no better than fake surgery, and still showed no benefit ten years later.2
- Traumatic knee tears (a specific fall, twist, or injury): surgery has a stronger case, but one major trial found that starting with physical therapy worked just as well as immediate surgery, and about 6 in 10 still hadn’t needed surgery two years later.3
- Rotator cuff repair (stitching a torn rotator cuff tendon) is a different operation from the shoulder surgery in those trials. One study found 97% of repair patients would have it again two years later, though it left out anyone who had a complication or a second surgery.4 A Norwegian trial that randomly assigned people to repair or physical therapy found the two did about the same at two years, but repair pulled ahead after that for small and medium tears, and it was still ahead 15 years later.5
- In most of the trials that compared them, conservative care performed about as well as surgery. Rotator cuff repair is the exception. So the question isn’t “surgery or nothing.” It’s: was the conservative care you tried actually addressing the right problems?
Was your conservative care actually meaningful?
Not all conservative care is created equal. Most people who end up in a surgeon’s office already tried physical therapy, and when it didn’t work, it was easy to conclude conservative care just wasn’t the answer.
I’d push back on that conclusion.
Not on the research. Not on physical therapists. But on the standard approach they’re trained to follow. It’s focused on the joint that hurts, and often doesn’t look at problems above or below it that may be setting that joint up for failure. That may be why you were disappointed with the process.
I told this to another patient just the other day, who’d come to me for sciatic pain. She’d had a knee replacement and was still seeing a PT for post-surgical rehab but was unhappy with it. I explained to her that it’s not that her therapist was bad: they treated the joint exactly the way they were trained to. The problem is that the standard approach doesn’t necessarily ask why the knee isn’t functioning well in the first place.
— Rick’s case notes
What standard physical therapy looks like
See for yourself. These are the typical goals of physical therapy for these problems, from the patient sites of the American Physical Therapy Association and the American Academy of Orthopaedic Surgeons:6, 7
- Reduce pain and swelling
- Restore range of motion
- Strengthen the muscles around the joint
- Walk without favoring the leg, and return to daily activities, work, and sport
The surgeons’ Rotator Cuff and Shoulder Conditioning Program is a good standard example, and it does include exercises for the muscles that move the shoulder blade.7 The APTA’s guideline for meniscus and cartilage problems fits the same picture: it recommends strengthening the knee and hip muscles, and its recommended exam focuses on the knee.8
These are reasonable goals that are measurable, and that’s important so the PT knows improvement is happening and for insurance reimbursement. In my experience, these programs help most people. No argument there. But look at what they’re built around: the joint that hurts. What’s missing is an assessment of why that joint may be overloaded, leading to the tear or pain in the first place:
- How the hip, ankle, shoulder blade, and mid-back are positioned and moving
- How the joint works when you walk, bend, climb stairs, reach into a cabinet: how you move, not just how fast or how far
- Getting up from a chair, vacuuming, getting out of the car
That’s the gap. I understand that many of these things are also included in many PTs’ care, but that leaves it up to the therapist to decide, which, in my mind, introduces doubt that everything that should be done, was done. The guidelines say as much themselves: they aren’t meant to be a standard of care, and the final judgment rests with the clinician.8, 9 My sciatic patient wasn’t unhappy with bad care; she was unhappy with the standard approach, followed correctly.
There’s also a second question to consider: who actually delivered your care?
- Physical therapists now graduate with a doctorate.
- Physical therapist assistants have an associate’s degree and work under a PT’s supervision.
- In busy clinics, you might see the PT once, for the evaluation, and an assistant for nearly every visit after that.
This may come into play when so much of the plan depends on the PT’s judgment. In one large study, patients whose care was delivered mostly by assistants or aides averaged about two more visits and finished with lower function scores.10
I tried this model myself, in my own clinic. Scaling with PTAs made financial sense (I’d even considered aides too, since they’re cheaper still), but I was never satisfied with the level of care being delivered, and that might say more about my hiring skills than about their ability to do the job well. Either way, I couldn’t make the model work financially while holding the standard I wanted, and it’s one of the biggest reasons I sold my clinic.
Component thinking vs. systems thinking
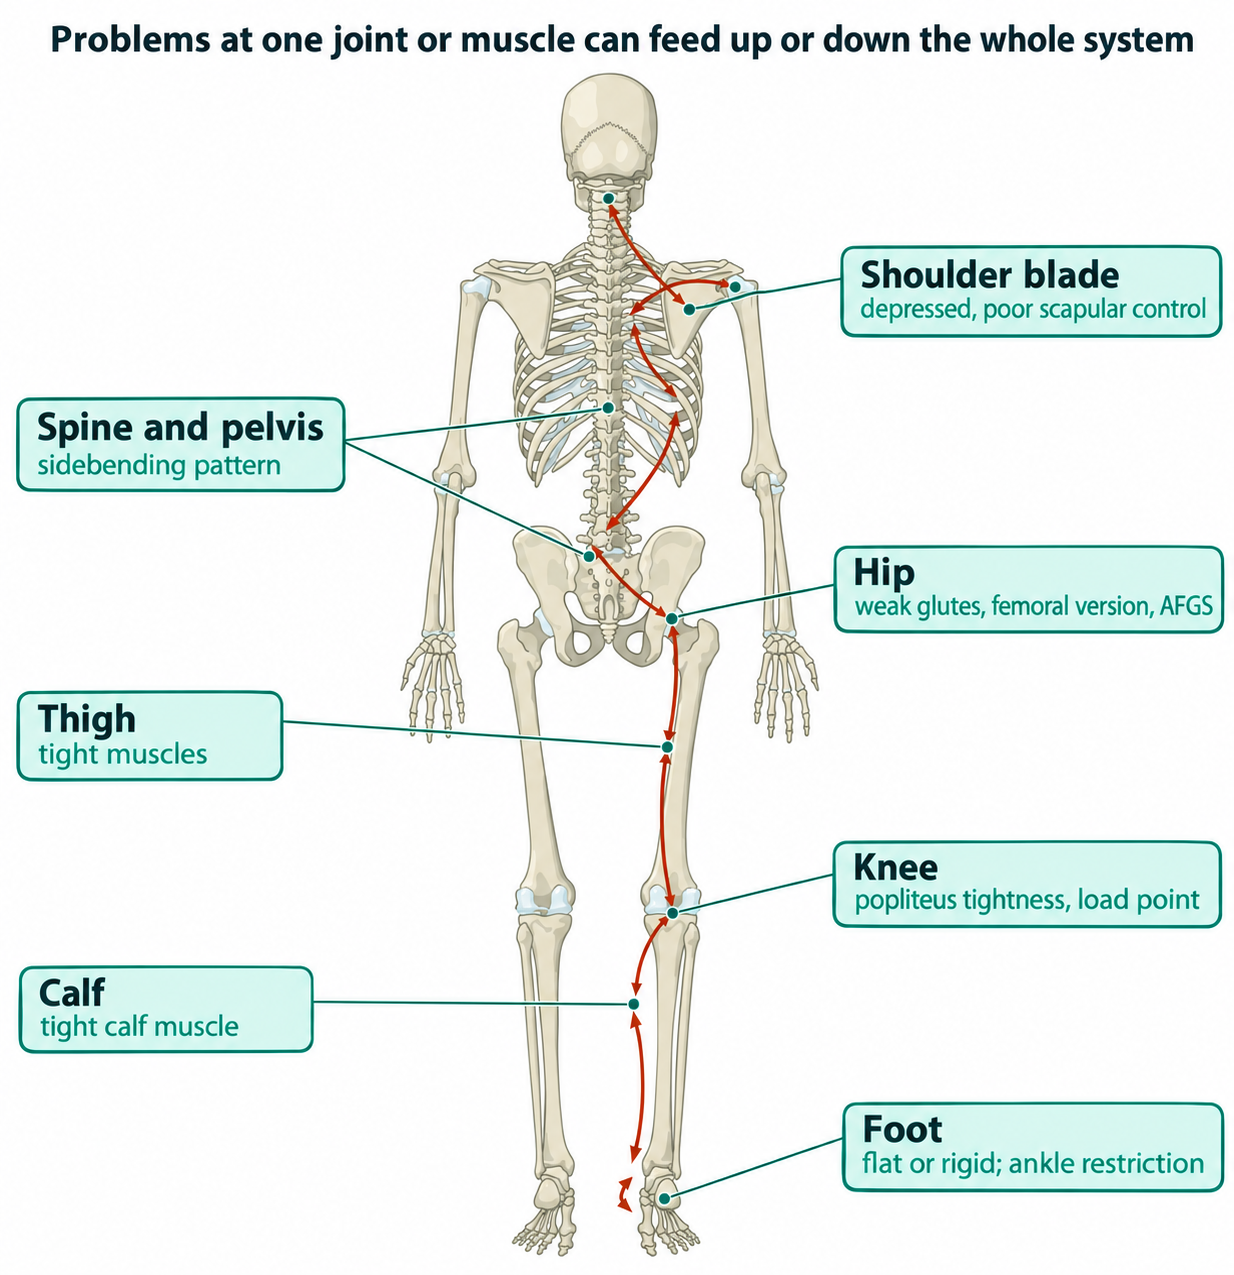
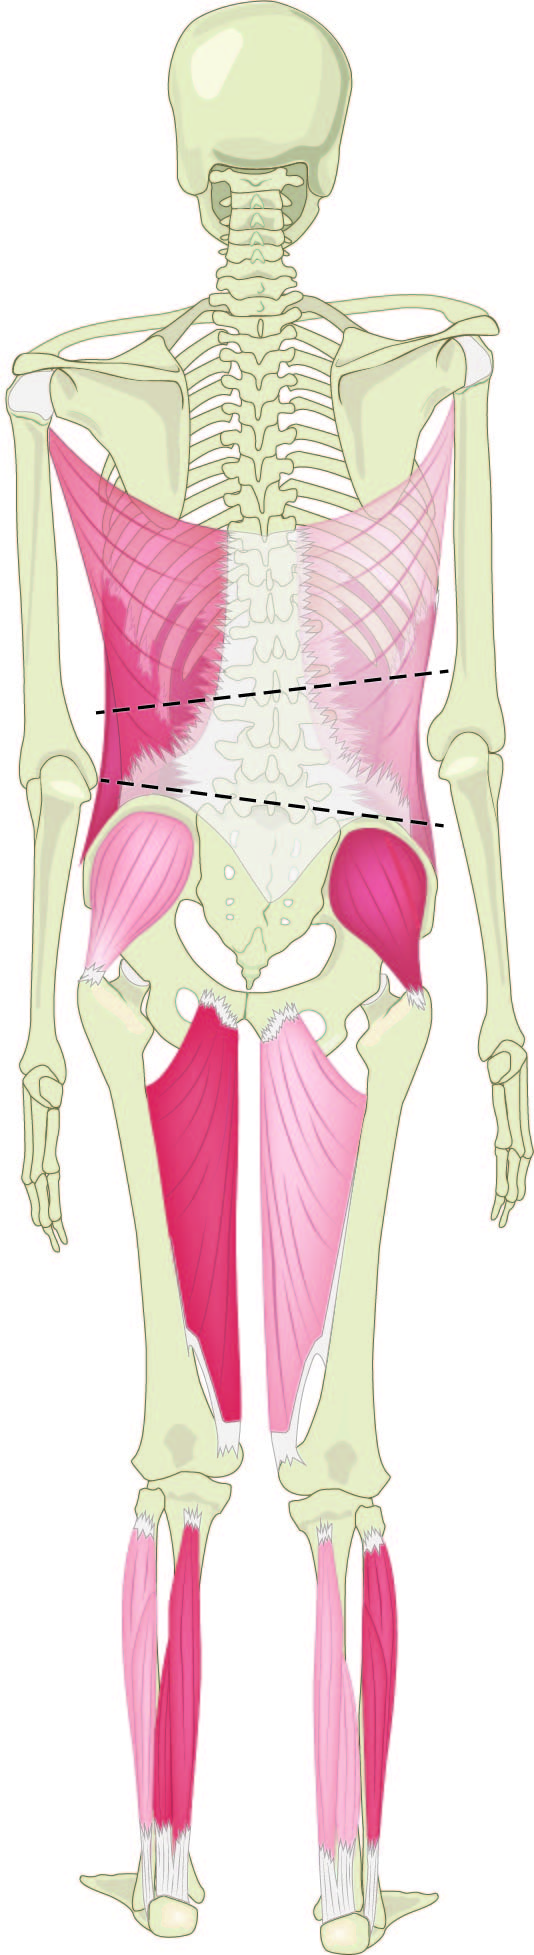
I think of the standard above as an example of component thinking. Treat the joint in front of you: get the knee or shoulder to bend and straighten well, and make sure there’s decent strength. In my experience, this works very well for acute injuries, but not so well for chronic problems. And many degenerative cases are actually chronic problems.
Instead, I use systems thinking, which incorporates how each joint affects the ones above and below it.
Schools don’t seem to teach this in a meaningful way, and there’s a reason. Medical research proves or disproves an effect by isolating one variable. It’s great at “does strengthening this muscle help this joint,” and not very good at how ten things happening at once across the body add up to someone’s pain. Many of the studies cited here left out people who had other problems at the same time. My massage therapist patient is a good example. Along with his tear, he had a stress fracture in the bone just beneath the joint surface.
Our bodies work as systems. Research mostly doesn’t.
So systems thinking never made it into the curriculum, not because it’s wrong, but because it’s difficult to generate this type of research due to its very nature.
That’s why I read the surgery-vs-conservative-care trials cited earlier with one question in mind: what did the conservative care actually include? Where the trials describe it, it was solid, standard care:*
- In a Norwegian trial, everyone did the same 12-week strength and balance program, two to three supervised sessions a week.1
- In a US trial, physical therapy followed a knee-focused protocol of swelling control, hands-on work, strengthening, and balance, for about six weeks.1
- In the trial of younger people with injury-related tears, physical therapy was a knee-focused three-phase program, with a median of 8.5 sessions.3
- In the Finnish fake-surgery trial, both groups got the same home exercise program after surgery.1
Several of these programs included hip strengthening. None described assessing what was driving each person’s knee problem: the hip, the foot, or the way they walk.
In one of the newest trials, adding in-clinic physical therapy (hands-on work around the knee and more strengthening of the same muscles) to a home exercise program didn’t reduce pain any further.11 The researchers were careful about what that means:
The researchers’ own caution
Their findings “should not be extrapolated beyond the specific regimens investigated.”11
In my view, more of the same isn’t the same as targeting what’s driving the problem. And yes, sometimes knee pain from a meniscus tear is just that: a torn meniscus. But what I’m talking about is figuring out if there were problems that led to that meniscus being vulnerable to a tear in the first place.
So the accurate reading is that these specific programs did about as well as surgery. That’s good news. My honest belief is that a systems-thinking approach might tip those results further toward conservative care.
This isn’t a knock on physical therapists. It’s about training, which is why I built a 30-hour CEU course that teaches this systems approach to all pain in the body.
What I actually check
(and my YouTube video links if you want to check yourself)
Knee
- Gait: how you actually walk.
- Hip and glute firing pattern: people with knee arthritis tend to have weaker hips,12 and in my experience weak or poorly-timed glutes overload the knee (see Figure 3 · read more).
- Foot and ankle mechanics: changes how force travels up before it hits the knee.
- Femoral version: thigh bone angle in the hip socket (watch the test · read more).
- Popliteus tightness: a small forgotten muscle behind the knee that’s a commonly overlooked source of ongoing knee pain (watch · read more).
- Pelvis and rib cage level: uneven often means one leg isn’t working right (watch the test · read more).
- Compensation: is the painful knee the problem, or is the other leg forcing it to overload? (watch the test · read more).
- Standing habits: equal weight on both legs? Does one knee lock more?
- Anterior femoral glide: does the thigh bone move correctly in the socket? True AFGS testing needs a practitioner, but weak glute function, shown in the video above, is usually the giveaway that it’s present.
The hip research measured how hard the hip muscles could push in a testing position. A muscle can test strong and still not turn on when you walk or climb stairs, depending on how you’re using your body. In my experience, that’s the more important question, along with how the pelvis and trunk are positioned. I go deeper into what these studies measured, and what they missed, in my hip pain and knee pain articles.
Shoulder
- Shoulder blade position and mechanics: there are rules about how the shoulder blade rests and moves (watch below · read more).
- Serratus anterior function: a key muscle moving and stabilizing the shoulder blade; when it’s not doing its job, the whole shoulder mechanism suffers.
- Sidebending pattern: the rib cage matters because the scapula rests on it (watch the test · read more).
- Trapezius function: precise, or just present?

WatchShoulder Pain: 5 Landmarks & 2 Exercises
I measure where the shoulder blade sits at rest and where it ends up once the arm is overhead. Early research supports focusing on the shoulder blade, though the evidence is low certainty.9
When my patient came to me, I ran him through all of this (except for the shoulder blade screen). He’d been my patient years earlier, and I hadn’t seen him since. In that time he’d built my recommendations into his own training, and it showed:
- Glutes: fired nearly perfectly
- Strength: strong almost across the board, without the weakness I usually find after an injury
- Compensation: none
- Structure: neutral thigh bones, not hypermobile, so no built-in factors his training needed to work around
- Popliteus (the small muscle behind the knee I find involved in so much stubborn knee pain): no tenderness at all (read more)
- Calf and soleus: a little tighter on the injured side
That dashed my hopes for a miraculous recovery.
I was happy to see a lower body system working that well. It also made my job harder, because there was very little left for me to change. That’s part of figuring these things out: sometimes there’s no hidden driver to find, and an injury is just an injury. My recommendations came down to a knee brace for stability, and a night splint to gently lengthen his calf and soleus. I wanted to address everything I possibly could.
Over the months, his program included clamshells, standing leg lifts, and two of my own exercises, butt pumps and Neanderthal lunges. The lunges, which I’d given him years earlier for a different problem and he’d kept doing ever since, made his pain worse. He also tried stationary biking, complete rest, taping, the brace, and the splint.
Nothing exotic. Just looking under every possible rock for clues.
If you have an inkling that your conservative care could have been more complete, try the tests in the videos above before you decide about surgery.
If you’ve decided to move forward with surgery
If you’ve already decided to have surgery, this part is about doing it well, starting with your pre-op consultation.
Five things to ask before you go in
Take these to your pre-op consultation
- Check the research yourself. Go to pubmed.ncbi.nlm.nih.gov and search your procedure plus “outcomes.” Look for randomized trials and systematic reviews near the top, and read who was included and excluded, so you know whether you resemble the people studied. Ten minutes, and you’ll walk into your consultation more informed than most patients.
- Know whether you’re degenerative or traumatic, and what that changes. Ask your surgeon which one they think you are. The evidence for surgery is weakest for degenerative tears and stronger, though not automatic, for traumatic ones.
- Ask whether they’re repairing or removing the tissue. This is the question I’ve asked my patient to take to his surgeon. Trimming out the torn piece and stitching it back together lead to different long-term outcomes. How often arthritis developed or progressed:
One type of meniscus tear in middle-aged patients: 51% after removal vs. 21% after repair13
Tears caused by an injury (a study cited in the APTA’s knee guideline): 40% after removal vs. 20% after repair8
Both looked back at past patients rather than randomly assigning them, so part of the gap may come from who was chosen for each surgery.
For the shoulder, the question looks a little different. With a rotator cuff tear, it’s usually whether to repair the tendon at all, and for small and medium tears the long-term research favors repair.5 If the plan includes a subacromial decompression, shaving bone to make more room for the tendons, remember that it did no better than a fake operation.2
Often the surgeon can’t make this call until they’re inside the knee or shoulder and can see the condition of the tissue and its blood supply. I’ve seen this happen often with my own patients. In one trial, surgeons switched to a meniscus repair partway through the operation in about 1 in 12 cases.3 MRIs also miss things: in two of the fake-surgery trials, close to 1 in 10 people turned out at surgery to have something different from what the scan and exam suggested.1, 2 So ask what they’ll do in each case, and why. If removal is the plan, ask why repair isn’t possible.
- Ask for specifics. What percentage of patients still have pain after two years? What percentage eventually need a joint replacement?
- Ask what “successful” actually means to them. Function, pain relief, or both? A surgeon can speak with confidence about what exactly their procedure will do. Pain is a different question entirely, and no one can anticipate your body’s reaction to the surgery: inflammation, pain, infection, spasm, or none of these.
What happened to me
A couple of years ago I was trail running, fell, and tore my shoulder labrum, a SLAP tear. I did the work: months of rehab, movement patterns identified and addressed, before I ever decided on surgery. This was a traumatic injury, not some chronic underlying problem that went unaddressed.
I had the surgery. The surgeon trimmed the torn labrum, moved my biceps tendon to a new attachment point (a biceps tenodesis), and did a subacromial decompression, shaving bone to make more room in the shoulder. That last one is the same procedure that, in the two trials above, did no better than fake surgery for impingement pain. I didn’t know that research at the time. My rehab went well, ahead of schedule on every metric my surgeon tracked. My shoulder works a little better now, maybe 5 to 10 percent. But I have more pain now than I did before it.
— Rick Olderman
It just goes to show that you can do everything right and still have pain. But knowing I did everything right beforehand gives me peace of mind: this is the best outcome available to me. That matters. I can compartmentalize it.
It also exposed something in my own thinking. When I got that diagnosis, having surgery wasn’t really a decision I weighed. It just felt like what I needed to do. If a PT who’s spent three decades studying this didn’t know the research on arthroscopy’s risks going in, most people don’t either. That’s the reason this article, and the YouTube video I made about it, exist. With my current meniscus problem, I’m applying the wisdom from my previous shoulder surgery, along with this research, and waiting it out instead of jumping into surgery.
How to improve your outcome
The difference between component thinking and systems thinking doesn’t disappear just because you’re now post-surgical. If you’ve decided to move forward, here’s my advice: get together with your physical therapist beforehand and address every weakness and tightness issue affecting your function, as thoroughly as you can. Maybe even try those tests in my videos above to measure your function more broadly.
This serves two purposes. After surgery, the muscles around the joint can temporarily “switch off.” Researchers call it arthrogenic muscle inhibition, and it makes those muscles harder to activate. If you’ve already practiced activating those muscles beforehand, in my experience that connection tends to come back faster afterward, which speeds up your recovery.
Second, the more you fix your function before surgery, the clearer a baseline you have. That makes it much easier to tell, afterward, whether your function actually improved, and how much that mattered for your pain, instead of guessing.
Where this leaves you
Back to my patient. His decision comes down to three options, and they’re the same ones many readers face:
- Surgery now, knowing it might turn out to be a repair or a trim.
- More time, continuing the conservative care he’s already doing. For injury tears, one trial of people aged 18 to 45 found that the group who started with physical therapy, including the 4 in 10 who went on to have surgery, had the same knee function at two years as the group who had surgery right away.3 Trying conservative care first didn’t leave them worse off.
- Changing what he does for a while, so the knee pain can settle down without giving up activity entirely.
That third choice is the one I’ve made for my own knee. Instead of running, I’ve taken up swimming, which I’m very bad at. It keeps my cardio going while protecting the joint, and it gives my knee time to work things out.
None of this is about anyone hiding the long-term picture. Surgeons want to help their patients, and patients want relief now. I feel the same pull. Most of us, me included, aren’t great at weighing a long-term risk against a problem that’s bothering us today, especially when it’s our own body. Part of me wants to tell my patient to just get the surgery, because it might make him happy soonest. But I know that trimming the meniscus may speed up arthritis over the years that follow, and possibly lead to a knee replacement down the road.1 That knowledge comes with a responsibility to put the long-term picture on the table.
When my patient read a draft of this article, he asked me whether his tear was degenerative or traumatic. My guess is both. In my experience, a lot of tears in active adults happen this way: years of gradual wear, then one load too many. For him, it may have been heavy farmer’s carries on top of a lot of training. The stress fracture is the clue pointing me in this direction. That’s often overtraining, and I’m guilty of it myself. I didn’t adjust my training to my age, and my bones and soft tissue paid for it. I’ve since changed my program. My body is happier about that than my ego is.
If your situation is degenerative, the honest takeaway is that surgery probably isn’t your best first move, and a trial of meaningful conservative care should come first. If it’s a traumatic injury with a mechanical block, or repair is possible and conservative care has been tried, surgery becomes a far more reasonable option.
And sometimes, even after you’ve read all of this, rested, and given conservative care a thorough try, your short-term goals come first. Maybe you have a race coming up, or an event that means a lot to you. Then surgery may be the right choice for you at this point in your life, made knowing the potential long-term trade-off. Just know that faster relief isn’t guaranteed either: in one fake-surgery trial of knee arthritis, the real operation never relieved pain better than the fake one at any point, while another trial found a small early advantage that faded within a few months.1
At first blush, my patient’s decision looked simple: trim the tear, problem solved. Once you see what the research shows, it isn’t. It’s now been more than nine months. He has a surgery date on the calendar, but he’s recently started feeling better, and he’s back on the fence. It’s been a roller coaster. Whichever way he goes, he’s deciding with the whole picture, short term and long term. That’s what I want for you too.
Rick’s takeaway
In most of the trials that compared them, conservative care did about as well as surgery. So the question isn’t “surgery or nothing.” It’s whether the conservative care you tried was actually addressing the right problems. Whichever way you go, decide with the whole picture, short term and long term.
Frequently asked questions
Is arthroscopic surgery better than physical therapy?
For degenerative knee problems and shoulder impingement pain, not reliably.1, 2 For traumatic knee tears, surgery has a stronger case, though most people in one major trial did fine without it.3 For small and medium rotator cuff tears, the long-term research favors repair. As the authors of one 15-year trial put it, “while physiotherapy can be effective, long-term results from primary tendon repair are superior.”5
Can a meniscus tear heal without surgery?
The tear usually doesn’t disappear on a scan, but the pain and function connected to it often improve with the right conservative care, especially for degenerative tears.
When is arthroscopic knee surgery actually necessary?
The clearest case is a locked knee, where a torn piece physically blocks movement. Traumatic tears in younger, active people, especially repairable ones, come next. Degenerative tears are the weakest case for surgery as a first move.
Should I try physical therapy before arthroscopic surgery?
Yes, but make sure it’s the right kind: an evaluation of how your whole body moves, not just the joint that hurts. See what I actually check.
Is a degenerative meniscus tear different from a traumatic one?
Yes. A degenerative tear builds up gradually, with no single triggering event. A traumatic tear comes from a specific fall, twist, or impact. Some, like my patient’s, may be both. The research against surgery is strongest for degenerative tears.
Do these study results apply to my case?
Maybe. Trials choose their patients carefully. One major knee trial left out people with locked knees, repairable tears, ligament ruptures, and arthritis,3 and a large shoulder trial enrolled about 1 in 10 of the people it assessed.2 That cuts both ways: the team behind one fake-surgery trial picked the patients “most likely to benefit,” reasoning that if surgery couldn’t beat a fake operation in them, it was unlikely to do better in routine care.1 Ask your surgeon whether you resemble the people in the studies they’re relying on.
What should I ask my surgeon before agreeing to arthroscopy?
At minimum: whether your tear is degenerative or traumatic, whether they plan to repair or remove the tissue, and what “successful” means to them. The full list is above.
Can physical therapy prevent the need for arthroscopic surgery?
For many people with degenerative tears, yes, though not for everyone. In my view it’s underused as a first option. Rotator cuff tears are the exception: in one long-term trial, tears treated with physical therapy alone roughly doubled in size.5 I think that’s because the supraspinatus, the muscle most often torn, plays a part in just about every arm motion.
Want the full program?
Two starting points, depending on where it hurts
In one large trial, a home exercise program did as well as adding clinic visits.11 I built my knee program, 7 Days to Better Knees, as a home program too. It runs you through the same testing I use with in-person visits, then builds your corrective plan from your results, so everyone’s program is a little different. There’s no standalone shoulder program yet, but stubborn shoulder pain happens for the same reasons stubborn neck pain and headaches happen. So my 7 Days to Better Neck program is the one to start with. It’s built around shoulder blade mechanics. Watch the walkthrough video to see if it makes sense to you.
7 Days to Better Knees
Shoulder pain instead? Start with 7 Days to Better Neck.
Have a question this article didn’t answer?
Send it through the Ask Rick form. I read every question and use the most common ones to shape future articles, videos, and my monthly email — sometimes by featuring them, never with identifying details, in a public answer. I ask for your email in case I need more detail, or want to let you know when I’ve covered it.
References
- Knee trials.
Fake-surgery (sham) trials: Moseley JB, et al. “A Controlled Trial of Arthroscopic Surgery for Osteoarthritis of the Knee.” N Engl J Med. 2002;347(2):81-88. Knee arthritis; real arthroscopic surgery did no better than fake surgery for pain or function at any point over two years. View study · Sihvonen R, et al. (FIDELITY). “Arthroscopic Partial Meniscectomy versus Sham Surgery for a Degenerative Meniscal Tear.” N Engl J Med. 2013;369(26):2515-2524. Degenerative meniscus tear without arthritis; trimming the meniscus did no better than fake surgery at one year. At surgery, 14 of 160 knees (9%) had findings that didn’t match the MRI and exam, such as no medial tear or other damage, and were excluded (p. 2517). View study · Sihvonen R, et al. Br J Sports Med. 2020;54(22):1332-1339. Five-year follow-up: no benefit, slightly more arthritis progression and more catching or locking symptoms after trimming; the authors say they chose patients “most likely to benefit” and that knee symptoms in a worn knee “are not necessarily attributable to meniscus tissue” (p. 1337). View study · Kalske R, Sihvonen R, et al. N Engl J Med. 2026;394(17):1757-1759 (letter). Ten-year follow-up: no benefit and signs of worse outcomes after trimming, including more meniscus-related symptoms; 11% vs. 4% went on to knee replacement or realignment surgery. View study
Surgery vs. physical therapy or exercise: Kirkley A, et al. N Engl J Med. 2008;359(11):1097-1107. Knee arthritis; surgery plus physical and medical therapy was no better than the same therapy alone at two years; the surgery group had a small advantage at three months that the authors call “transient” (p. 1104). View study · Katz JN, et al. (METEOR). N Engl J Med. 2013;368(18):1675-1684. Meniscus tear plus arthritis, age 45+; no significant difference in function at six months; 30% of the physical therapy group had surgery by then. View study · Kise NJ, et al. BMJ. 2016;354:i3740. Degenerative meniscus tear, ages 35-60; 12 weeks of supervised exercise did as well as surgery at two years. View study
Clinical guideline: Siemieniuk RAC, et al. BMJ. 2017;357:j1982. Strong recommendation against arthroscopy for nearly all patients with degenerative knee disease. View study
The exercise programs: the full programs used in the Kise and Katz trials are in each paper’s supplementary appendix. Kise supplement, Figure S1 · Katz supplement, Table 2 These are good exercise programs that work most of the muscles around the knee, and if you haven’t tried an exercise program, they’re a good place to begin. Check with your doctor or physical therapist first, since each was designed for a specific group of patients. What I’d add, from my clinical experience, is an assessment of what’s driving the knee’s breakdown, which these programs weren’t built to address.
↩ a b c d e f g h i j - Shoulder decompression trials (shaving bone and tissue to make more room for the tendons, in people without a full-thickness rotator cuff tear). Beard DJ, et al. (CSAW). The Lancet. 2018;391:329-338. Real surgery was no better than fake surgery; 313 of 2,975 people assessed took part. View study · Paavola M, et al. (FIMPACT). BMJ. 2018;362:k2860. Real surgery was no better than fake surgery or supervised exercise at two years. 12 of 134 patients who had the arthroscopy (9%) were excluded because the surgeon found problems the MRI hadn’t shown, such as full-thickness rotator cuff tears. View study · Kanto K, Bäck M, et al. (FIMPACT, 10-year follow-up). BMJ. 2025;391:e086201. Still no benefit over fake surgery or exercise at ten years; all three groups improved substantially. View study
↩ a b c d e f - van der Graaff SJA, et al. (STARR). Br J Sports Med. 2022;56(15):870-876. Traumatic meniscus tears, ages 18-45; starting with physical therapy (with surgery available later) did as well as immediate surgery at two years; 41% of the physical therapy group had surgery during those two years. Excluded locked knees, tears suitable for repair, ligament ruptures, and arthritis. In 4 surgery patients (8%), the surgeon switched to a meniscus repair during the operation based on what they saw (p. 873). View study
↩ a b c d e f - Khan AZ, et al. J Clin Med. 2024;13(9):2550. 92 patients two years after rotator cuff repair at one institution: average satisfaction 9 out of 10, and 96.7% would have the surgery again. Patients with a complication or second surgery were excluded, as were those who didn’t complete their follow-up questionnaires; no comparison group. View study ↩
- Moosmayer S, Lund G, Seljom US, et al. “Fifteen-Year Results of a Comparative Analysis of Tendon Repair Versus Physiotherapy for Small-to-Medium-Sized Rotator Cuff Tears: A Concise Follow-up of Previous Reports.” J Bone Joint Surg Am. 2024;106(19):1785-1796. 103 people (average age about 60) with full-thickness rotator cuff tears 3 cm or smaller, randomly assigned to tendon repair (an open or mini-open repair, with bone shaved from the acromion) or to individually adapted physiotherapy, with later surgery available. Results were similar at two years; after that the gap grew in favor of repair, mainly because results in the physiotherapy-only group slowly declined as their tears enlarged (front-to-back tear width grew from about 16 mm to 32 mm). At 15 years, repair led to less pain and better shoulder function; quality-of-life scores didn’t differ. 15 of 51 physiotherapy patients (29%) had surgery later, so most never needed it; because those 15 were still counted in the physiotherapy group, the comparison understates the gap between repair and physiotherapy alone. The physiotherapy-only patients showed little interest in further treatment, which the authors suggest reflects effective coping. 63% of the people assessed weren’t included. View study
↩ a b c d - American Physical Therapy Association, ChoosePT.com. “Physical Therapy Guide to Meniscal Tear.” Source of the knee goals list. View page ↩
- OrthoInfo (American Academy of Orthopaedic Surgeons). “Rotator Cuff and Shoulder Conditioning Program.” Source of the shoulder goals list; includes shoulder blade strengthening exercises. View page · “Knee Conditioning Program.” View page
↩ a b - Logerstedt DS, Scalzitti DA, Bennell KL, et al. “Knee Pain and Mobility Impairments: Meniscal and Articular Cartilage Lesions, Revision 2018.” J Orthop Sports Phys Ther. 2018;48(2):A1-A50. The current APTA guideline; written mainly for post-surgical care. Recommends progressive strengthening of the knee and hip muscles; its recommended exam is knee-focused. Cites a study of injury-related tears (Stein et al., 2010) in which arthritis progressed in 40% after meniscus removal vs. 20% after repair, 5 to 8 years after surgery; only about half the patients returned for that follow-up (p. A11). States it is “not intended to be construed or to serve as a standard of medical care.” View guideline
↩ a b c - Desmeules F, Roy JS, Lafrance S, et al. “Rotator Cuff Tendinopathy Diagnosis, Nonsurgical Medical Care, and Rehabilitation: A Clinical Practice Guideline.” J Orthop Sports Phys Ther. 2025;55(4):235-274. Recommends against using instruments to measure the shoulder blade’s movement because those measurements are unreliable, while reporting high-quality evidence for measuring its upward rotation at rest (p. 245). Reports low-certainty evidence that shoulder-blade-focused programs reduce pain and disability more than standard exercise in the medium term (pp. 260-261). States it is “not intended to formally set a standard of care” (p. 238). View guideline
↩ a b - Resnik L, Feng Z, Hart DL. “State Regulation and the Delivery of Physical Therapy Services.” Health Serv Res. 2006;41(4 Pt 1):1296-1316. 63,900 outpatients in 2000-2001; care delivered mostly by physical therapist assistants or aides was linked to about two more visits and lower function scores at discharge. Observational, so it shows an association, not proof of cause. View study ↩
- Katz JN, Collins JE, et al. (TeMPO). “A Randomized Trial of Physical Therapy for Meniscal Tear and Knee Pain.” N Engl J Med. 2025;393(17):1694-1703. 879 people aged 45-85 with a meniscus tear and knee arthritis; adding standard in-clinic physical therapy (or fake physical therapy) to a home exercise program didn’t reduce pain more at three months, and all groups improved substantially. View study
↩ a b c - Deasy M, Leahy E, Semciw AI. “Hip Strength Deficits in People With Symptomatic Knee Osteoarthritis: A Systematic Review With Meta-analysis.” J Orthop Sports Phys Ther. 2016;46(8):629-639. People with knee arthritis had weaker hip muscles than healthy people, especially for hip abduction. Measured maximum strength only; the authors say it’s unknown whether the weakness causes knee arthritis or results from it. View study ↩
- Hurmuz M, Ionac M, Hogea B, Miu CA, Tatu F. “Osteoarthritis Development Following Meniscectomy vs. Meniscal Repair for Posterior Medial Meniscus Injuries: A Systematic Review.” Medicina. 2024;60(4):569. Six mostly retrospective studies, 298 patients with one type of medial meniscus tear, average age about 55: arthritis progression in 51% after removal vs. 21% after repair. View study ↩
* The trials that included a physical therapy arm describe it as delivered by physical therapists. None I’m aware of describe assistants delivering the care, though I can’t say how every session was staffed. ↩
Research reviewed: October 2026