Hips · test
Femoral anteversion and retroversion: the hip pain factor almost no one tests for
Not all thigh bones are shaped the same. Some twist slightly inward, some twist outward, and that shape changes how your hip, knee, and back should move.
Licensed orthopedic physical therapist with 30 years of clinical experience, former owner of an
orthopedic PT clinic, and author of the Fixing You book series, including
Fixing You: Hip & Knee Pain and the award-winning Pain Patterns
(2025 NIEA Award winner). He created an APTA-approved continuing education course teaching other
clinicians his systems-thinking approach to chronic pain.
Most hip pain evaluations check the joint, the muscles around it, maybe your gait. The actual shape of your thigh bone isn’t routinely assessed — and that shape changes how everything else on the list should be treated.
The piece potentially driving your hip pain
If you’ve read the first two articles in this hip series, you already know that a lot of hip pain traces back to your glutes losing control of the head of the thigh bone in the socket — anterior femoral glide syndrome. What we haven’t covered yet is why some people’s glutes are fighting an uphill battle from the start.
Not all thigh bones are shaped the same. Some are naturally twisted inward at the hip, a shape called femoral anteversion. Others are twisted outward, called femoral retroversion. Neither shape is a problem by itself. But if you don’t know which one you have, and you move as though your thigh bone is neutral, you’re fighting your own anatomy every single step.
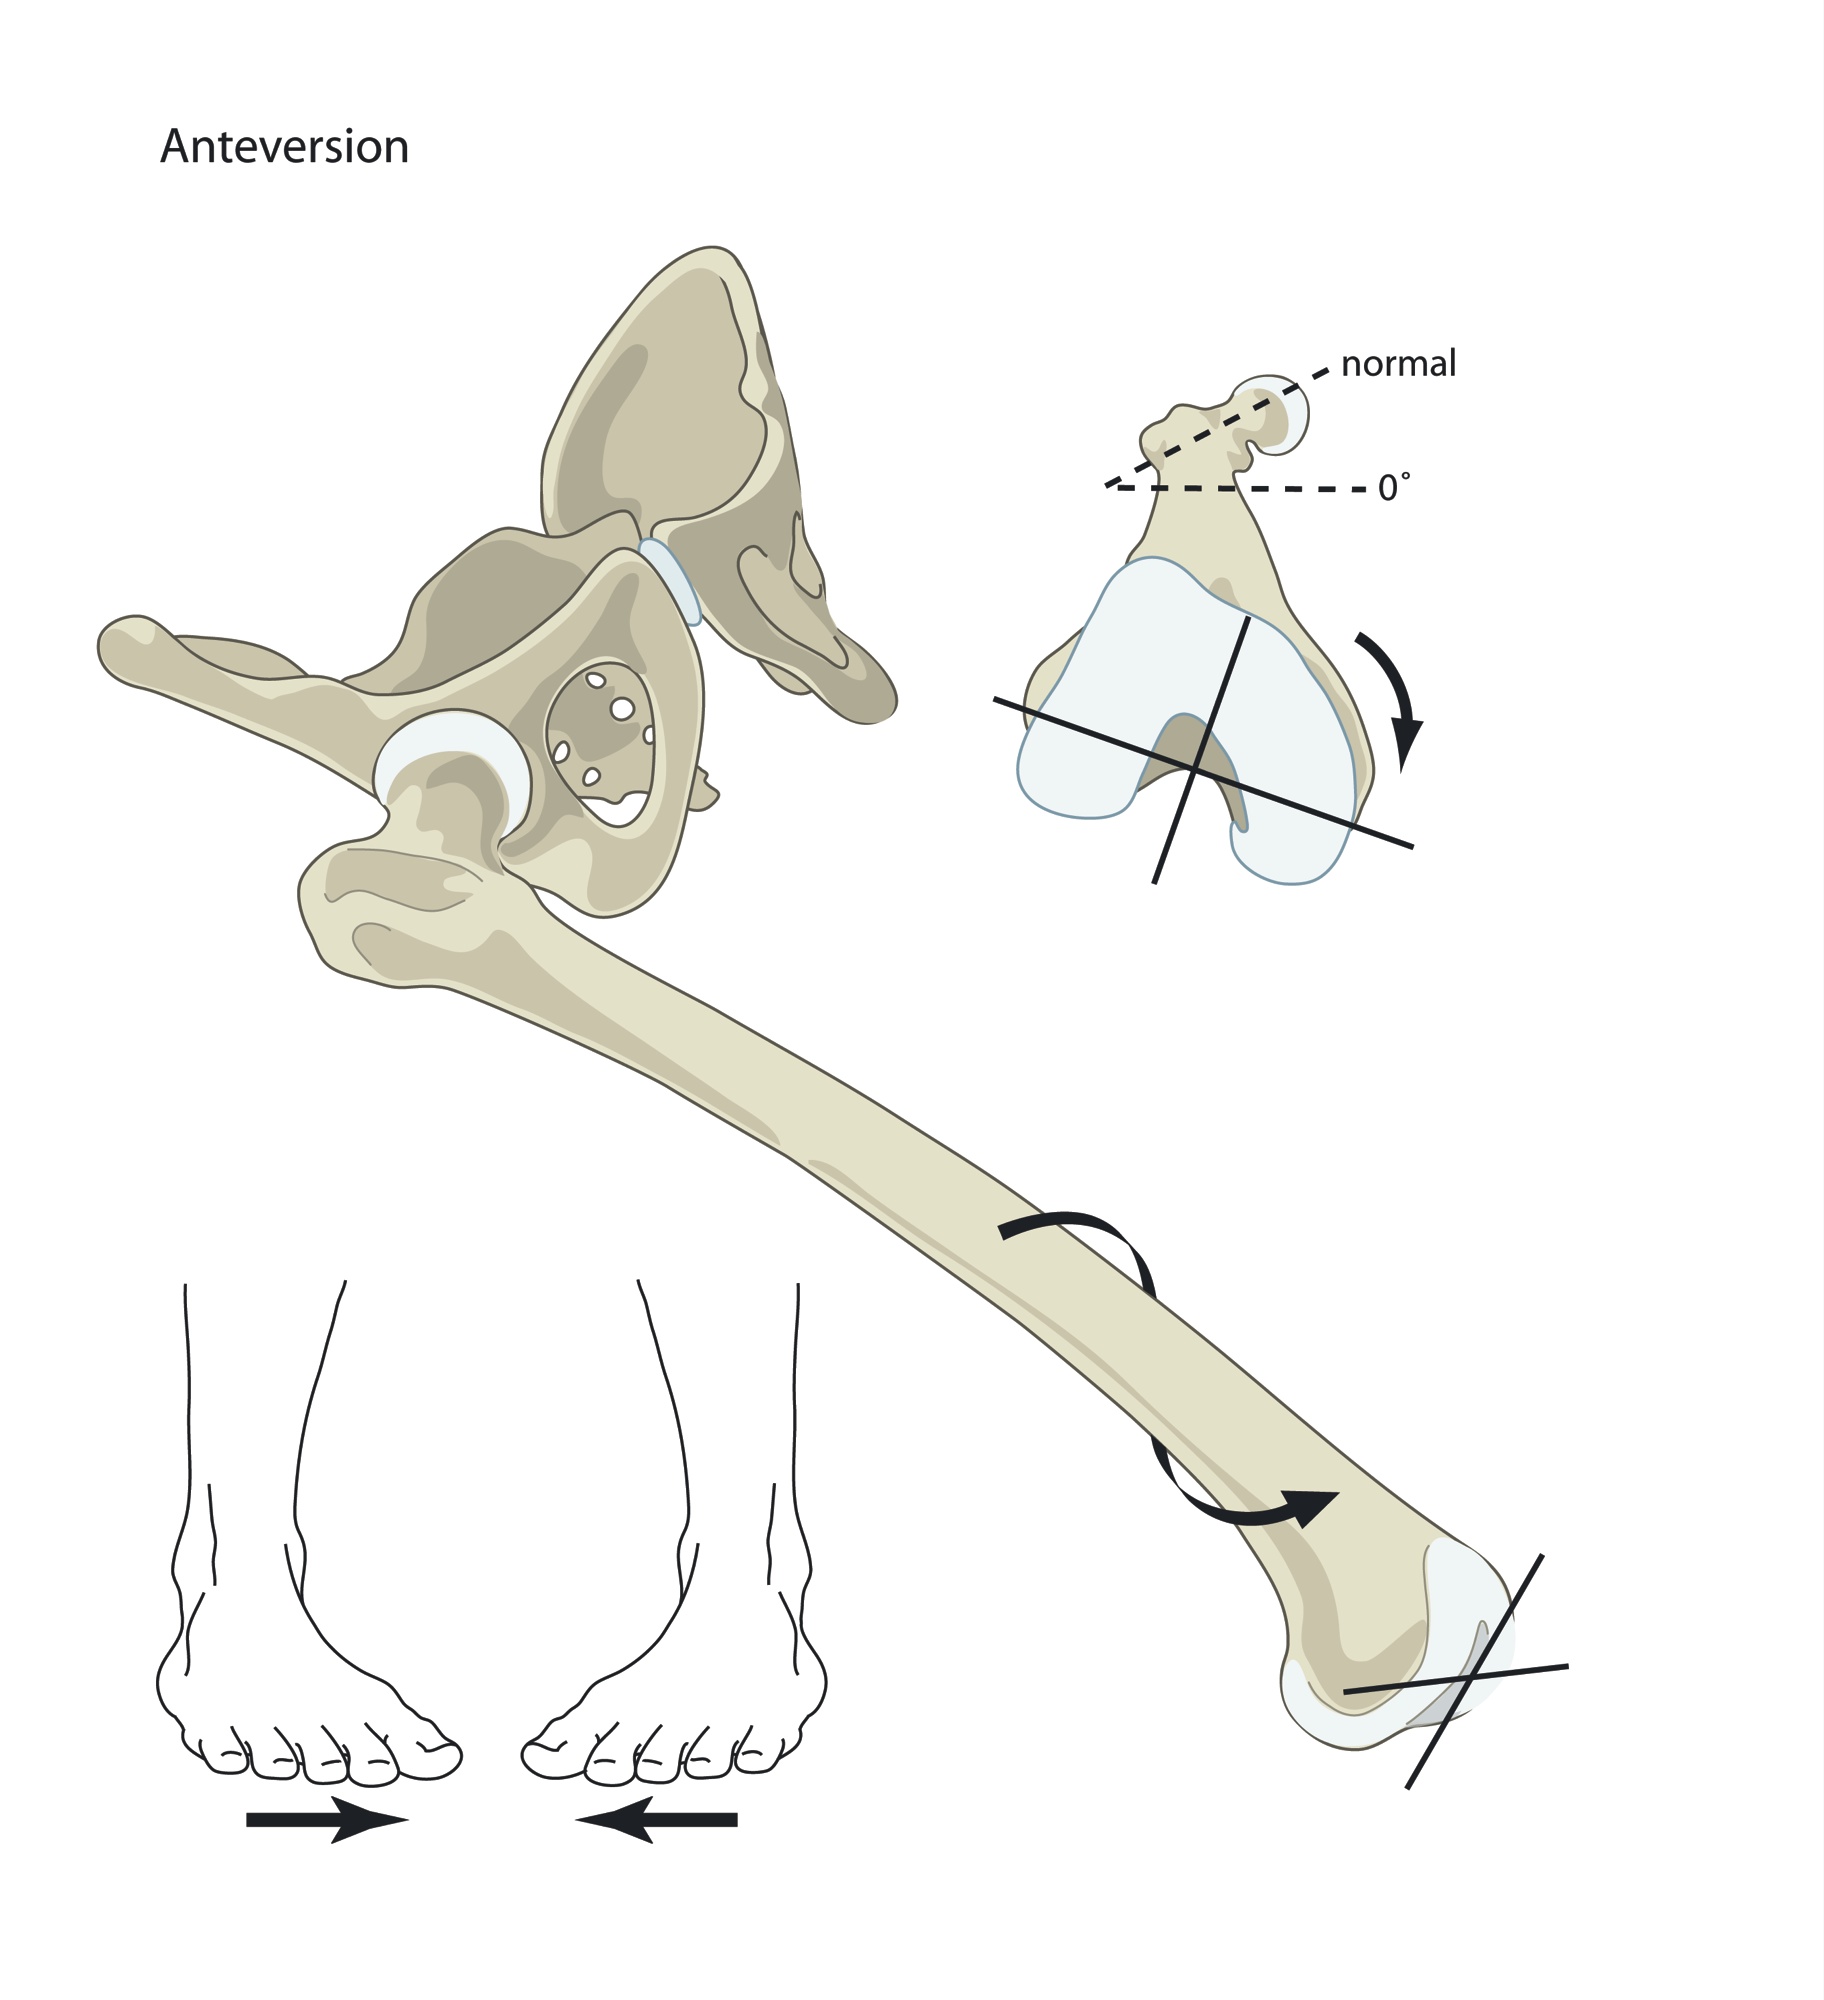
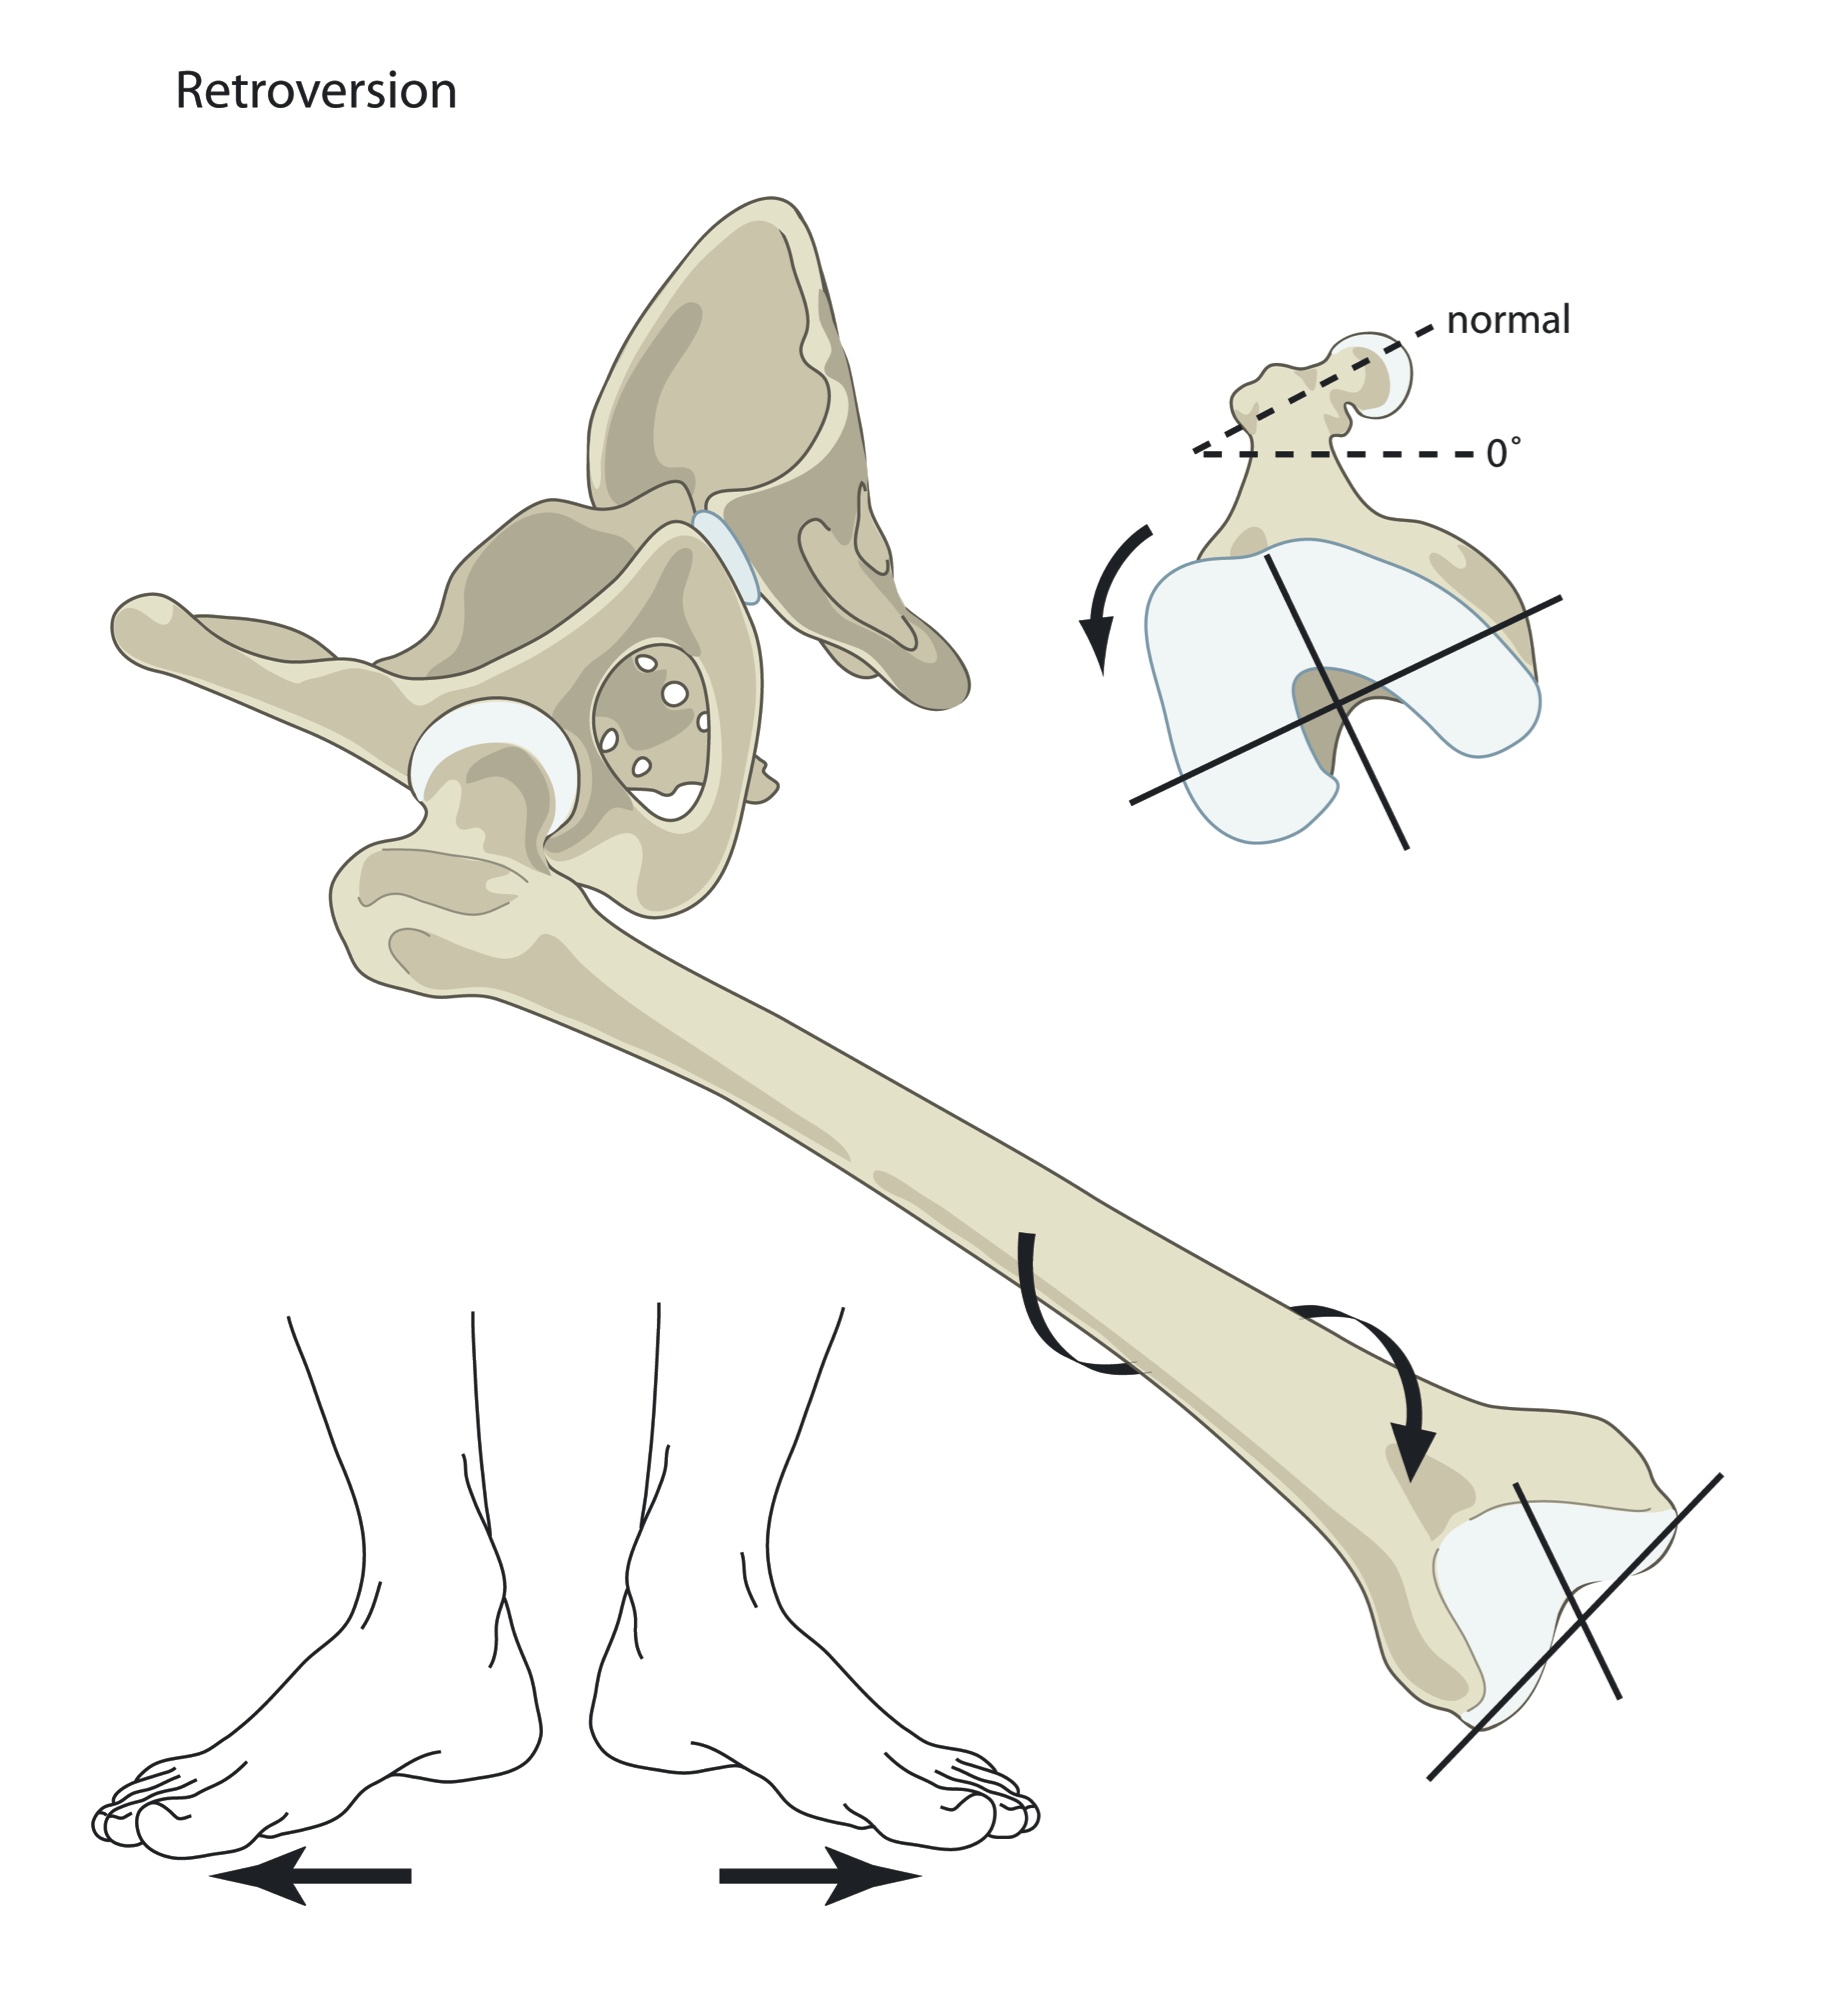
Always follow the guidance of your medical team. What follows isn’t a diagnosis. Femoral anteversion and retroversion are normal anatomical variations, not conditions, and this article is about how to move well given your own shape — not about correcting it.
Watch the video version
The self-test below, demonstrated.
The self-test: which shape do you have?
Quick take: Lying face down and letting your lower legs fall to each side shows you, in about a minute, whether your thigh bones are rotated inward, outward, or roughly neutral.
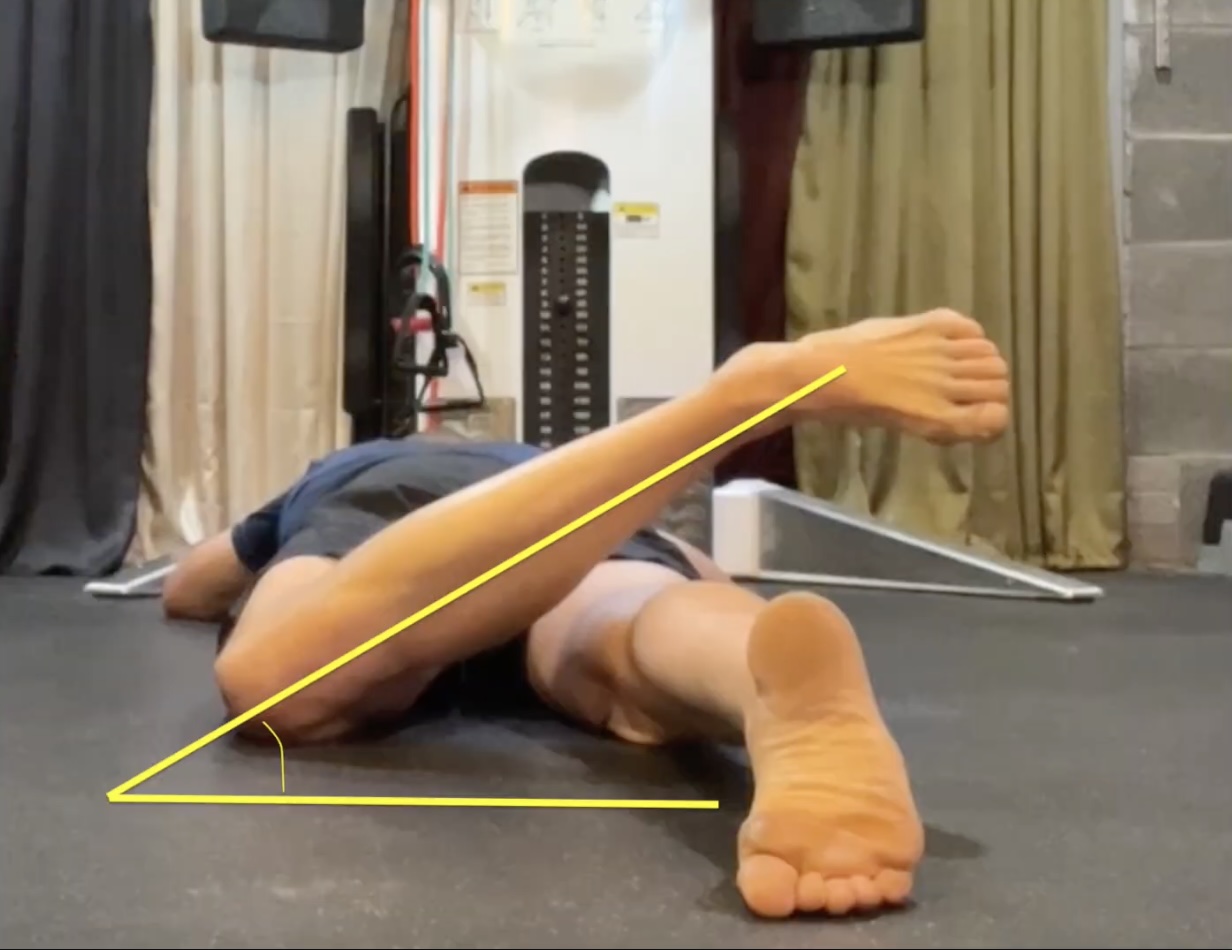
This test isn’t as accurate as having a clinician or MRI measure for you, but it can give you a useful clue about whether your femur may be more internally or externally oriented. It’s best to either video yourself or ask someone to take pictures of your angles so you can assess them.

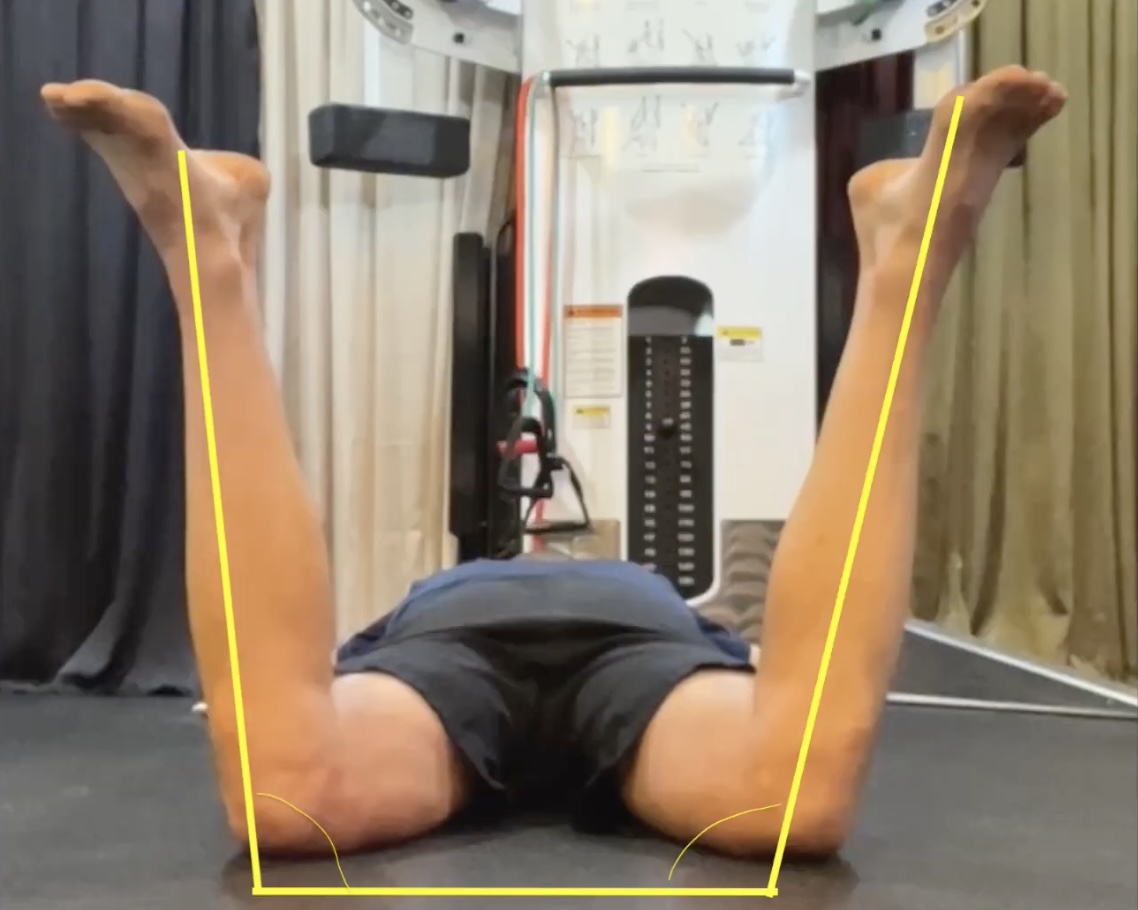
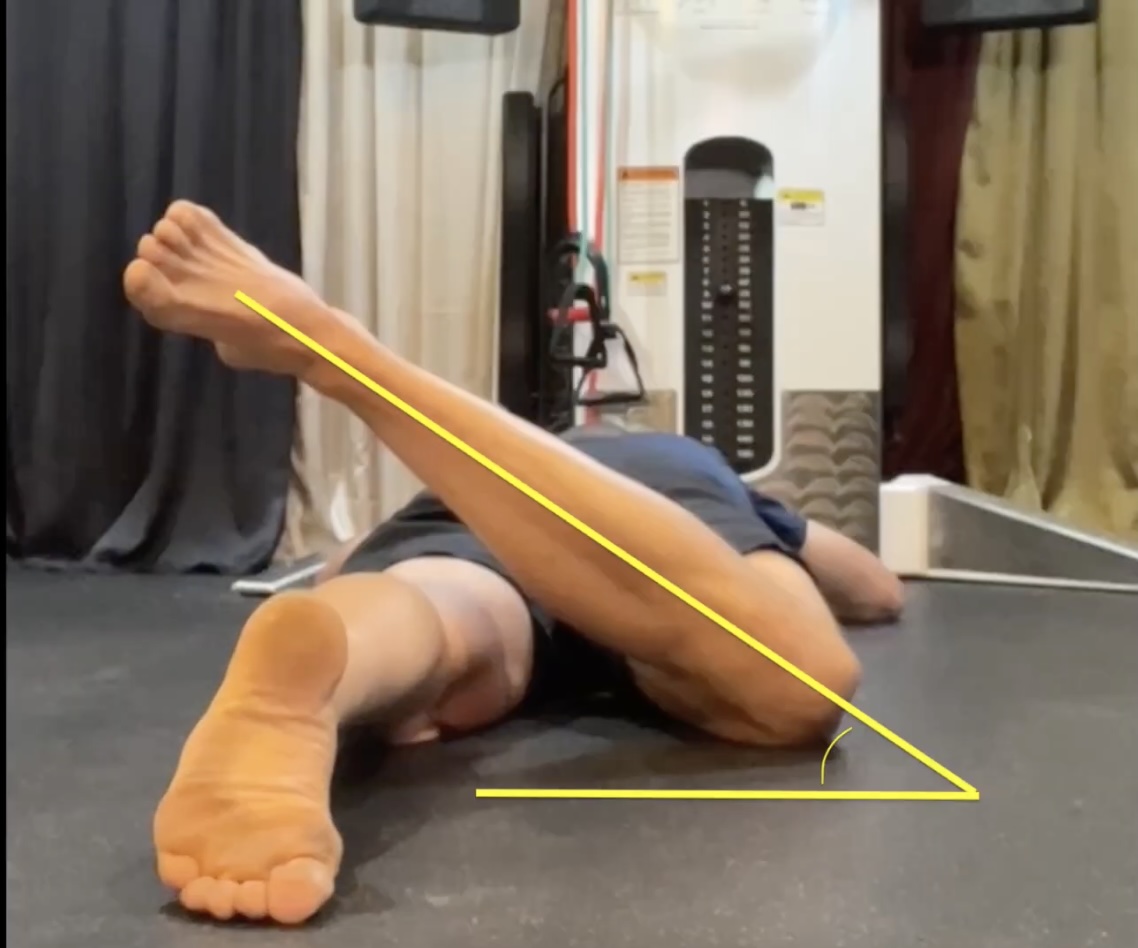
Try this test
Which way does your thigh bone twist?
- Lie on your stomach and bend both knees so your feet point toward the ceiling.
- Let your lower legs fall out to the sides. Note how far they fall.
- Straighten one leg, then let the other foot fall inward, across the midline, toward the back of your other knee. Don’t force it, and try not to let your pelvis twist to help it along. Repeat on the other side.
Reading your result. If your feet fall out much farther than they fall in, your thigh bone rotates inward more easily than outward — that points to femoral anteversion. If your feet fall in much farther than they fall out, your thigh bone rotates outward more easily — that points to femoral retroversion. If in and out are roughly equal, your thigh bones are close to neutral.
It’s entirely possible to have one shape on one side and the opposite shape on the other, so don’t be surprised if your left and right results don’t match.
One particularly dramatic example from my practice: an NFL lineman I treated for chronic ankle and knee pain had exactly this asymmetry. Once I showed him how to use his legs better, according to his thigh bone shape, nine years of chronic pain melted away in about three weeks.
— Rick’s case notes
This isn’t only relevant if you have hip arthritis or a labral tear. It applies just as much to highly trained performance athletes. Elite competitors are often searching for a one or two percent edge over the field, and understanding how your own femoral shape should change your foot position, your stance, and your movement strategy can have real implications for performance, not just for pain.
What are femoral anteversion and retroversion, and why do they matter?
Femoral anteversion means your thigh bone is naturally rotated inward at the hip. Femoral retroversion means it’s rotated outward. Both are normal variations in how the thigh bone develops, described in the movement-impairment literature by researcher Shirley Sahrmann.1
Neither shape is inherently a problem. The trouble starts when you move as though everyone’s thigh bone is neutral, because most people — and most of the advice they get — assume exactly that. In my clinical population, I see femoral version play an important role surprisingly often in people with persistent hip, knee, back, and foot problems, since the knee sits directly in the path of whatever rotation the thigh bone contributes. I cover that connection specifically in my knee pain article.
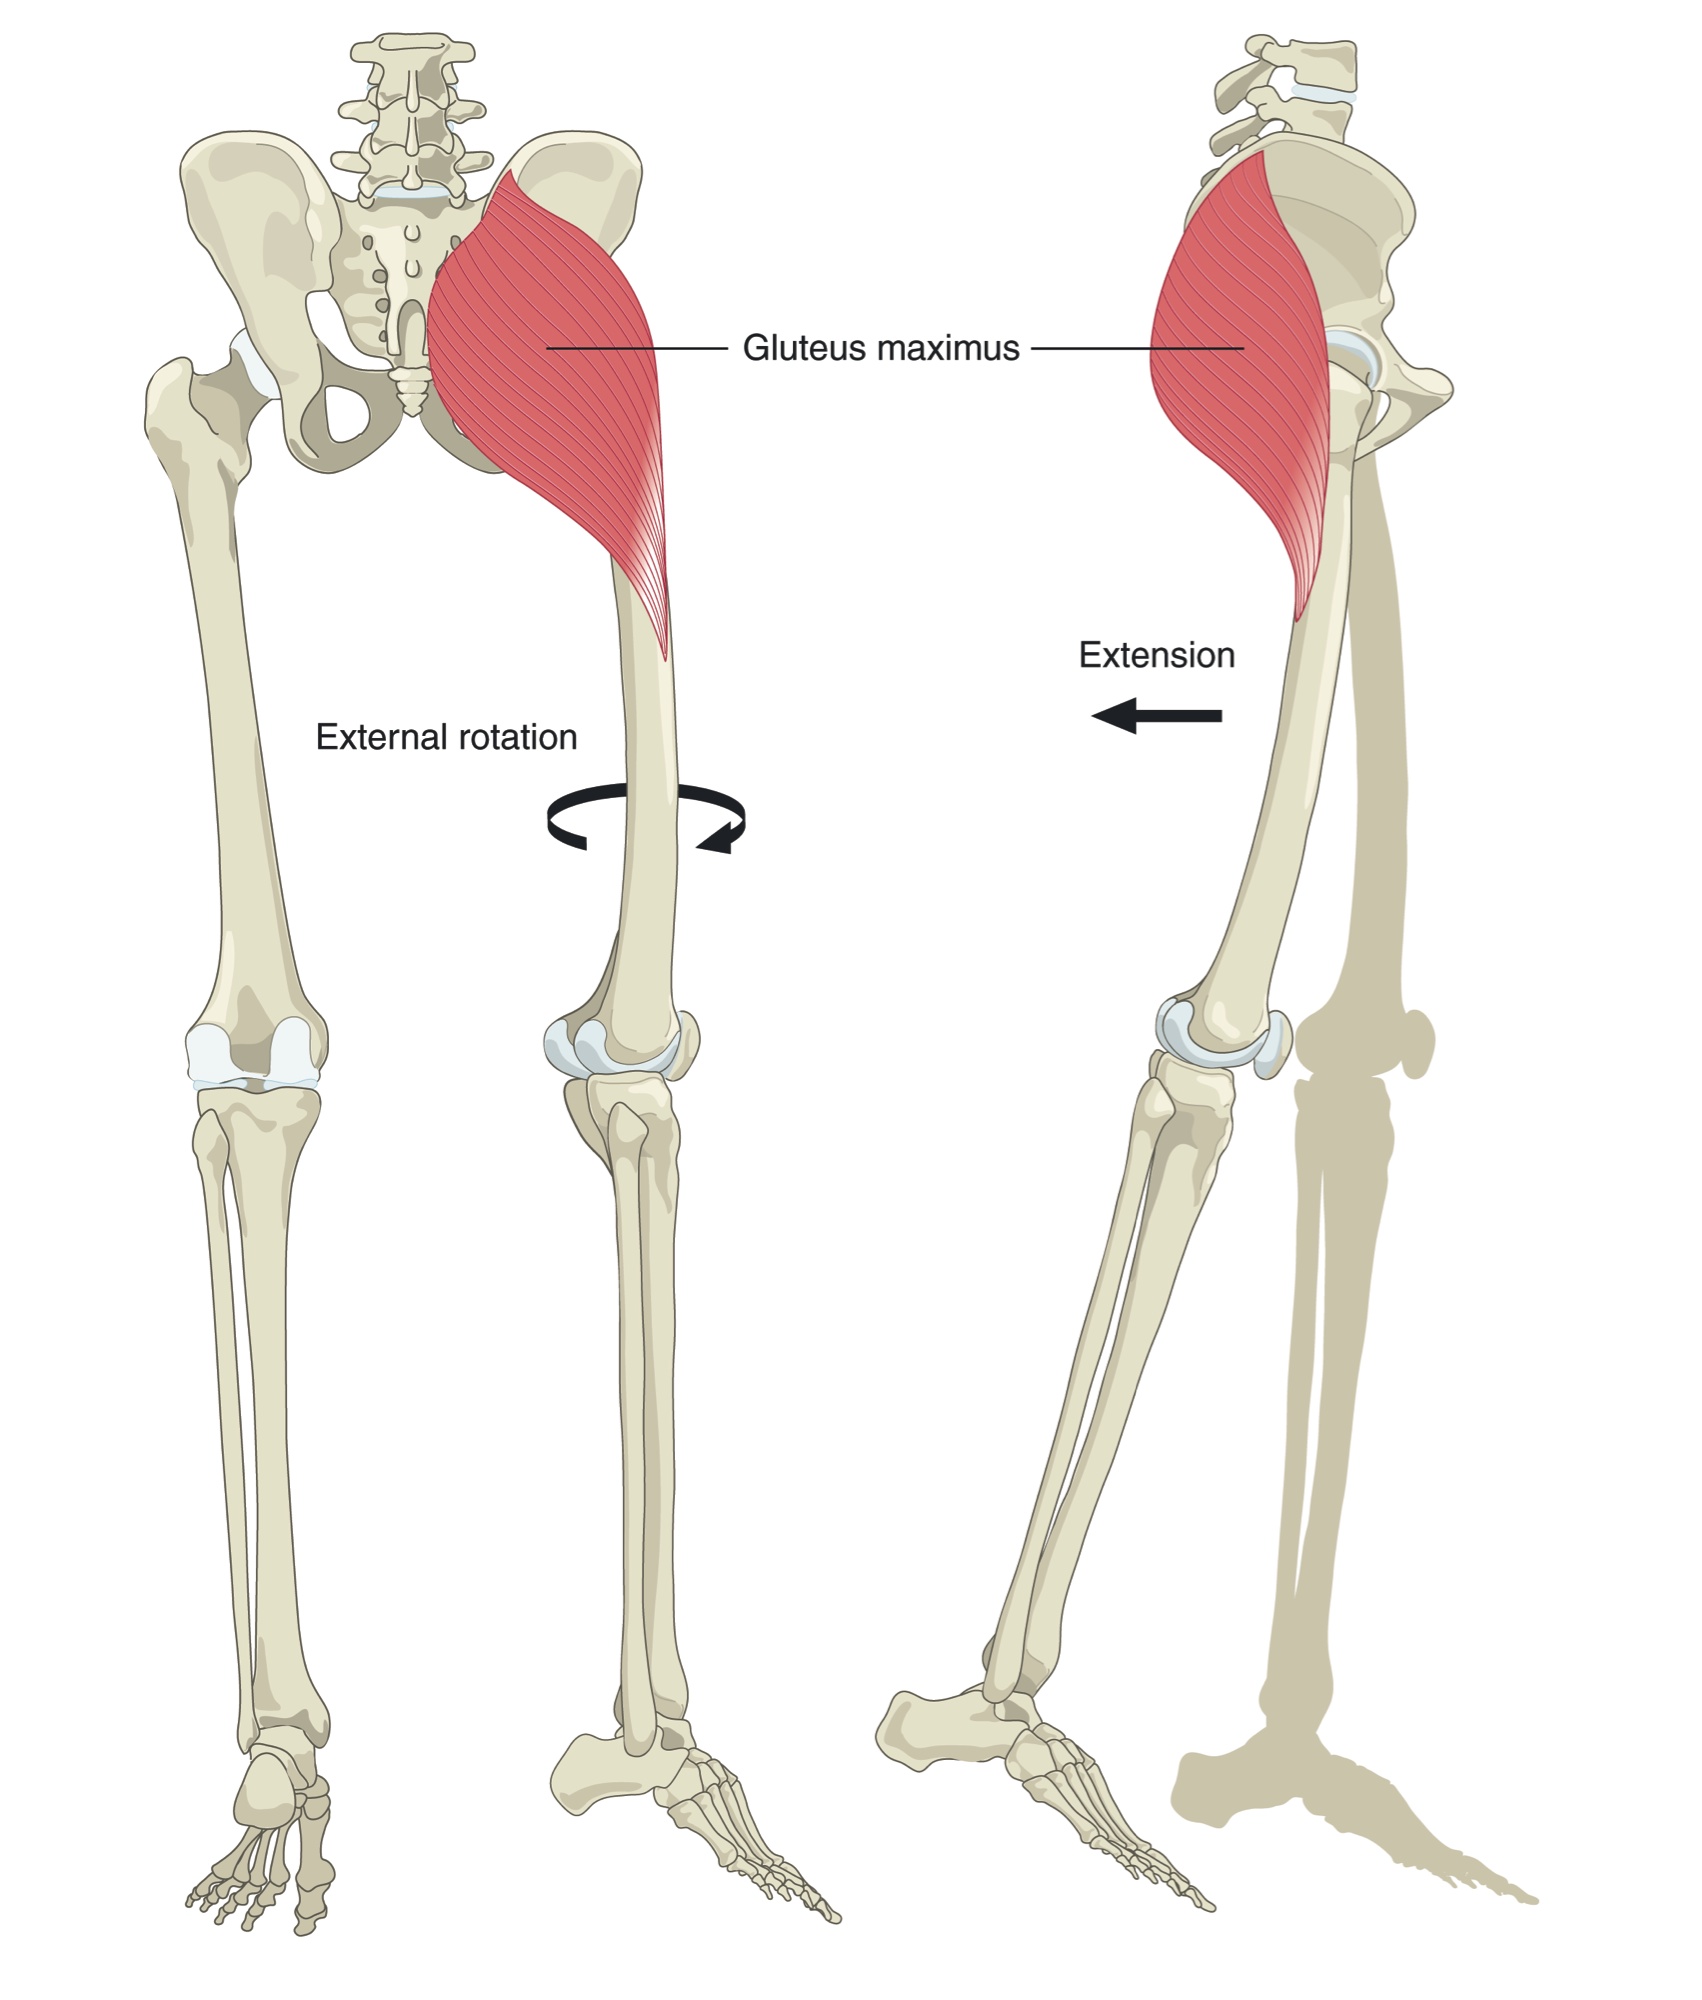
Because the gluteus maximus contributes to external rotation, an internally oriented femur changes the mechanical position in which the muscle has to work.2 Think of trying to lift a heavy weight with a biceps curl: the straighter your elbow at the beginning, the harder it is for the biceps to lift it. In my clinical experience, some people with anteversion need considerably more gluteal control to keep the femur from collapsing further inward during weight-bearing.
Retroversion — an externally rotated thigh bone — creates a different problem. These people should point their feet out to the side a few degrees to align foot position with thigh bone shape. But they often feel self-conscious walking with their feet turned out, frequently called “walking like a duck,” so they force their feet to point straight ahead. That recreates the excessive internal rotation problem described above, just by a different route.
Clinically, I see femoral anteversion in more females and femoral retroversion in more males. Average anteversion tends to run somewhat higher in women than in men in several studies too — roughly 18 degrees versus 14 degrees in one commonly cited series3 — though findings across studies vary. Retroversion is also relatively common in the general population, found in over a fifth of white men and in more than 14% of women across ethnic groups in one large trauma-center study.4
If you have femoral anteversion
Quick take: An inward-rotated thigh bone starts your glutes at a mechanical disadvantage. The fix is building enough glute strength to control that internal rotation, not fighting the shape itself.
Why this causes pain. Since the gluteus maximus externally rotates the thigh, an already-anteverted femur asks that muscle to work from a lengthened position on every step. If the glutes can’t keep up, the thigh bone drifts into more internal rotation than the hip and knee joints tolerate well — feeding the same anterior femoral glide pattern covered in the first article, and increasing compression at the hip and knee.
I had one patient with poorly controlled right femoral anteversion who had developed hip, knee, and new low back pain — his right leg visibly rotating inward every time he stepped on it. Once we addressed the glute control behind it, his pain resolved in two to three sessions. (Watch that case.)
— Rick’s case notes
Sylvia, whose story opened the first article, also had anteverted femurs. Because her thigh bones were already rotated in, she needed stronger glutes than most people to control that internal rotation — which is part of why her butt pump exercise eventually progressed to 15 to 20 pounds of ankle weight rather than stopping at bodyweight.
What to do
If your test pointed to anteversion
- Strengthen your glutes. The butt pump from the first article retrains this. If you can’t feel your glute engage, try rotating your knee slightly outward as you lift it — a cue I call “peeing on the fire hydrant.” It temporarily biases the glute to turn on. As you get stronger, work back toward doing the exercise without that rotation, since that’s closer to how you’ll actually walk.
- Reprogram your gait using the tiptoe-walking cue from the first article. An anteverted thigh bone makes consistent glute activation during walking even more important than it is for someone with a neutral femur.
- Experiment with your feet turning out. This biases the glutes to turn on. Once they get going, you can always turn them back in again, as long as the butt muscles are working.
If you have femoral retroversion
Quick take: An outward-rotated thigh bone means your feet naturally want to point slightly outward too. Forcing them straight ahead recreates the same internal rotation stress anteversion causes, just by a different route.
Why this causes pain. With retroversion, walking with your feet pointed straight ahead — the socially expected position — requires relatively internally rotating an already outward-rotated thigh bone. That takes real, constant muscular effort, and it tends to create chronic tension through the inner thighs, hips, and low back, along with the same glute-shutdown pattern seen with anteversion. It’s like covering everything in cement, just much stiffer.
I had one patient with a retroverted femur who developed a labral tear in his right hip while habitually forcing his foot forward. I can’t prove the foot position caused the tear, but the mechanics were compelling enough that changing his foot position became an important part of his treatment. It had also shut off the glutes controlling that hip’s tracking. He’s since started turning that foot out significantly to get off the damaged tissue, and it worked — but by then the damage was already done. His left side also began developing new back pain, from weight-bearing more heavily on it while protecting the injured hip. (Watch that case.)
— Rick’s case notes
Research on femoral retroversion and hip damage is mixed. A systematic review found retroversion associated with hip pain and impingement, and reported it in 5 to 11% of patients who eventually needed a hip replacement, but the same review concluded the evidence that retroversion itself causes hip osteoarthritis is still weak.5 In my clinical experience, it’s less the shape itself and more what you do with it — specifically, forcing a retroverted leg into a foot-forward position — that seems to matter.
What to do
If your test pointed to retroversion
- Let your feet turn out. If your natural stance has your feet angled slightly outward, that’s likely your femur shape asking to be respected, not a posture problem to correct.
- Stretch your inner thighs, which tend to chronically tighten from years of holding a forced, unnatural foot position.
- Tiptoe walk to begin turning on the gluteals naturally while walking.
Putting it together
Anterior femoral glide syndrome, covered in the first article, is about how your thigh bone moves during activity. The compensation patterns covered in the second are about what happens to the rest of your body while you wait to fix any of this. Femoral anteversion and retroversion are the piece underneath both: the actual shape you’re working with before you take a single step. This is one pattern I see often — not the explanation for every case of hip, knee, back, or foot pain.
Knowing your shape informs how you should be using your lower body system to improve gluteal function and reverse the anterior femoral glide pattern. Someone with anteversion needs to build unusually strong glutes. Someone with retroversion needs to stop forcing their feet forward and let their natural stance do some of the work.
Rick’s takeaway
You can’t change the shape of your thigh bone, and you don’t need to. What you can change is whether you’re moving as though it’s shaped like everyone else’s — because that’s the part costing you a hip, a knee, or a back.
Across this series, you now have three pieces of the puzzle: the movement pattern, the compensation, and the anatomy. Knowing the pieces isn’t the same as knowing which ones apply to you and how they interact in your body. That’s what the testing throughout 7 Days to Better Hips and the Pain Patterns assessment are built to sort out.
Common questions
Can femoral anteversion or retroversion cause hip pain?
Neither shape is inherently painful. The question is whether the way you move interacts poorly with your particular anatomy. That interaction, not the shape itself, is what this article is about.
How do I know which one I have?
The self-test above gives you a useful first clue: lie on your stomach, let your legs fall out, then let each foot fall in and compare the two directions. For a precise measurement, a clinician or MRI is more accurate.
Can femoral anteversion or retroversion be corrected?
The bone itself generally isn’t something you correct with exercises. The goal is to understand your anatomy and adapt your movement and strength strategy to it, not to change the shape.
Can I still run, lift weights, or play sports with one of these shapes?
Yes. Neither shape rules out any activity. What changes is how you position your feet, and how much glute strength you need to control the rotation your specific shape creates.
Is femoral anteversion linked to ACL tears?
Femoral anteversion is more common in women, and female athletes face a 2 to 8 times greater risk of ACL injury than male athletes.6 I believe this is due, in part, to poorly controlled femoral anteversion creating excessive shear forces across the knee joint — the same mechanical disadvantage covered above. That’s my clinical belief connecting the two facts, not something a study has directly tested. A separate systematic review and meta-analysis looking specifically at anteversion and ACL biomechanics found the evidence inconclusive and didn’t support a clear sex-specific injury mechanism.7 I’d treat femoral anteversion as a plausible contributing factor worth addressing through gluteal control, not a proven cause on its own.
Should I avoid certain activities if I have one of these shapes?
Not avoid — adapt. Activities that demand a lot of hip rotation, like certain dance, martial arts, or pivot-heavy sports, deserve extra attention to glute control if you have anteversion, or to natural foot position if you have retroversion.
Is this the same thing as anterior femoral glide syndrome?
No, though they’re related, and I cover the difference in the first article in this series. Anterior femoral glide syndrome is about how your thigh bone tracks in your hip joint. Anteversion and retroversion are about the fixed shape of the bone itself, which can make anterior femoral glide more likely and harder to correct if it isn’t accounted for.
Can this affect my back and sciatica too, not just my hip and knee?
Yes. I cover this connection in more depth in my sciatica article, where femoral shape is one of several upstream drivers of what I call a sidebending problem.
I found one shape on one leg and a different shape on the other. Is that normal?
Yes, it’s common to have asymmetric femoral shape — one leg anteverted, one retroverted, or one clearly torsioned and the other closer to neutral. Treat each leg according to its own result.
If your self-test showed anteversion or retroversion
Test the whole pattern, not just the shape
7 Days to Better Hips includes testing for femoral torsion alongside the anterior femoral glide pattern covered earlier in this series, so you can see how the two interact in your own body.
Explore 7 Days to Better Hips
Want femoral shape in the context of the whole system? Pain Patterns walks through it in detail.
Some links in this article are affiliate links. If you buy through them I may earn a small commission, at no extra cost to you. I only recommend products I actually use with patients.
Have a question this article didn’t answer?
Send it through the Ask Rick form. I read every question and use the most common ones to shape future articles, videos, and my monthly email — sometimes by featuring them, never with identifying details, in a public answer. I ask for your email in case I need more detail, or want to let you know when I’ve covered it.
References
- Sahrmann SA. Diagnosis and Treatment of Movement Impairment Syndromes. St. Louis, MO: Mosby; 2002. Describes femoral anteversion and retroversion as movement-relevant anatomical variations within a systems-based framework. ↩
- Lewis CL, Sahrmann SA, Moran DW. “Anterior Hip Joint Force Increases with Hip Extension, Decreased Gluteal Force, or Decreased Iliopsoas Force.” Journal of Biomechanics. 2007;40(16):3725–3731. ↩
- Bråten M, Terjesen T, Rossvoll I. “Femoral Anteversion in Normal Adults: Ultrasound Measurements in 50 Men and 50 Women.” Acta Orthopaedica Scandinavica. 1992;63(1):29–32. Found average femoral anteversion of 18 degrees in women versus 14 degrees in men, though other studies have found smaller or no significant sex differences. ↩
- Koerner JD, Patel NM, Yoon RS, Sirkin MS, Reilly MC, Liporace FA. “Femoral Version of the General Population: Does ‘Normal’ Vary by Gender or Ethnicity?” Journal of Orthopaedic Trauma. 2013;27(6):308–311. Found femoral retroversion present in 21.4% of white men and over 14% of women across ethnicities studied. ↩
- Tsagkaris C, Dreher T, Zingg P, Rüger M. “Association of Femoral Retroversion and Out-Toeing Gait with Development of Hip Osteoarthritis and Treatment: A Systematic Review.” Acta Orthopaedica. 2025;96:356–362. Found retroversion in 5 to 11% of patients requiring hip replacement and associated with hip pain and impingement, but concluded the evidence that retroversion itself causes hip osteoarthritis remains weak. ↩
- Manfre MG, Richman EH, Araujo-Espinoza G, Frank RM. “Anterior Cruciate Ligament Injuries in Female Athletes.” Clinics in Sports Medicine. 2025. DOI: 10.1016/j.csm.2025.09.008. ↩
- Hogg JA, Waxman JP, Shultz SJ. “Examining the Effects of Femoral Anteversion and Passive Hip Rotation on ACL Injury and Knee Biomechanics: A Systematic Review and Meta-Analysis.” Journal of Experimental Orthopaedics. 2022;9:40. Found insufficient evidence to conclusively determine the effect of femoral anteversion on ACL injury risk, and no support for a sex-specific injury mechanism. ↩