Hips · start here
She canceled her hip replacement: here’s what changed her mind
Sylvia was scheduled for hip replacement surgery for worn cartilage, a labral tear, and bone spurs found on her MRI. A pattern called anterior femoral glide syndrome, and two simple corrections, changed her outcome.
Licensed orthopedic physical therapist with 30 years of clinical experience, former owner of an
orthopedic PT clinic, and author of the Fixing You book series, including
Fixing You: Hip & Knee Pain and the award-winning Pain Patterns
(2025 NIEA Award winner). He created an APTA-approved continuing education course teaching other
clinicians his systems-thinking approach to chronic pain.
Rest. Ice. Strengthen the muscles around the joint. That’s not wrong — it’s just treating the joint in isolation, instead of asking why your hip started failing in the first place.
If you’re weighing hip replacement surgery, you’re not alone
If hip pain has gotten bad enough that surgery has come up with your doctor, you already know the imaging can look alarming: worn cartilage, a labral tear, bone spurs, bone-on-bone contact. It’s natural to look at that and assume surgery is the only path forward.
Sylvia was in exactly that spot. Two surgeons recommended a hip replacement. She was walking with a cane and had given up kite surfing, tennis, gardening, and lifting weights.
She canceled the surgery soon after our session together. Here’s what she did instead.
Always follow the guidance of your medical team — they know your case better than an article can. What follows isn’t a diagnosis. It’s an explanation of how your body actually works, something to think about before you decide anything about surgery.
Watch the video version
I walk through the test, the exercise, and the habit change.
Sylvia’s story: from scheduled surgery to pain-free
Sylvia had hip pain for about a decade before it got severe enough, last winter, that she could barely walk without a cane. Both surgeons showed her the same imaging: worn cartilage, a labral tear, bone spurs. A hip replacement was scheduled.
In my clinical experience with her, the underlying driver was anterior femoral glide syndrome — the pattern this article covers. Years at a desk job had left her glutes essentially asleep, and her thigh bone was sliding forward in the joint every time she stood or walked.
She worked through my hip pain home program: glute pump exercises, eventually with 15 to 20 lbs of ankle weight, and correcting a locked-knee walking pattern using the tiptoe cue described later in this article. She canceled the surgery because her pain disappeared. She’s back to gardening, weight training, and dancing, pain-free. It’s now been four years and she’s still doing great.
— Rick’s case notes
Watch the full conversation: How Sylvia solved her hip pain in only six weeks.
Do I need hip replacement surgery for hip pain?
Not necessarily — at least not before ruling out a mechanical pattern first. Always follow your medical team’s recommendation for your case, but structural findings on an X-ray or MRI don’t automatically explain your pain: labral tears and cartilage defects show up at similar rates in hips with and without pain.1
A movement pattern called anterior femoral glide syndrome — your thigh bone sliding too far forward in the hip socket, first described by researcher Shirley Sahrmann2 — can drive pain on its own, touching everything from the front of the hip to the low back and sciatic nerve. A published case series found patients with this pattern achieved complete symptom resolution with conservative treatment alone.4
The common thread underneath much of it is glute muscles that aren’t doing their job. Here’s exactly how that plays out.
A common movement pattern behind hip pain
Quick take: Anterior femoral glide syndrome means the head of your thigh bone slides forward in the hip socket during standing, walking, and other everyday movement — and that forward slide stresses the tissue around your hip.
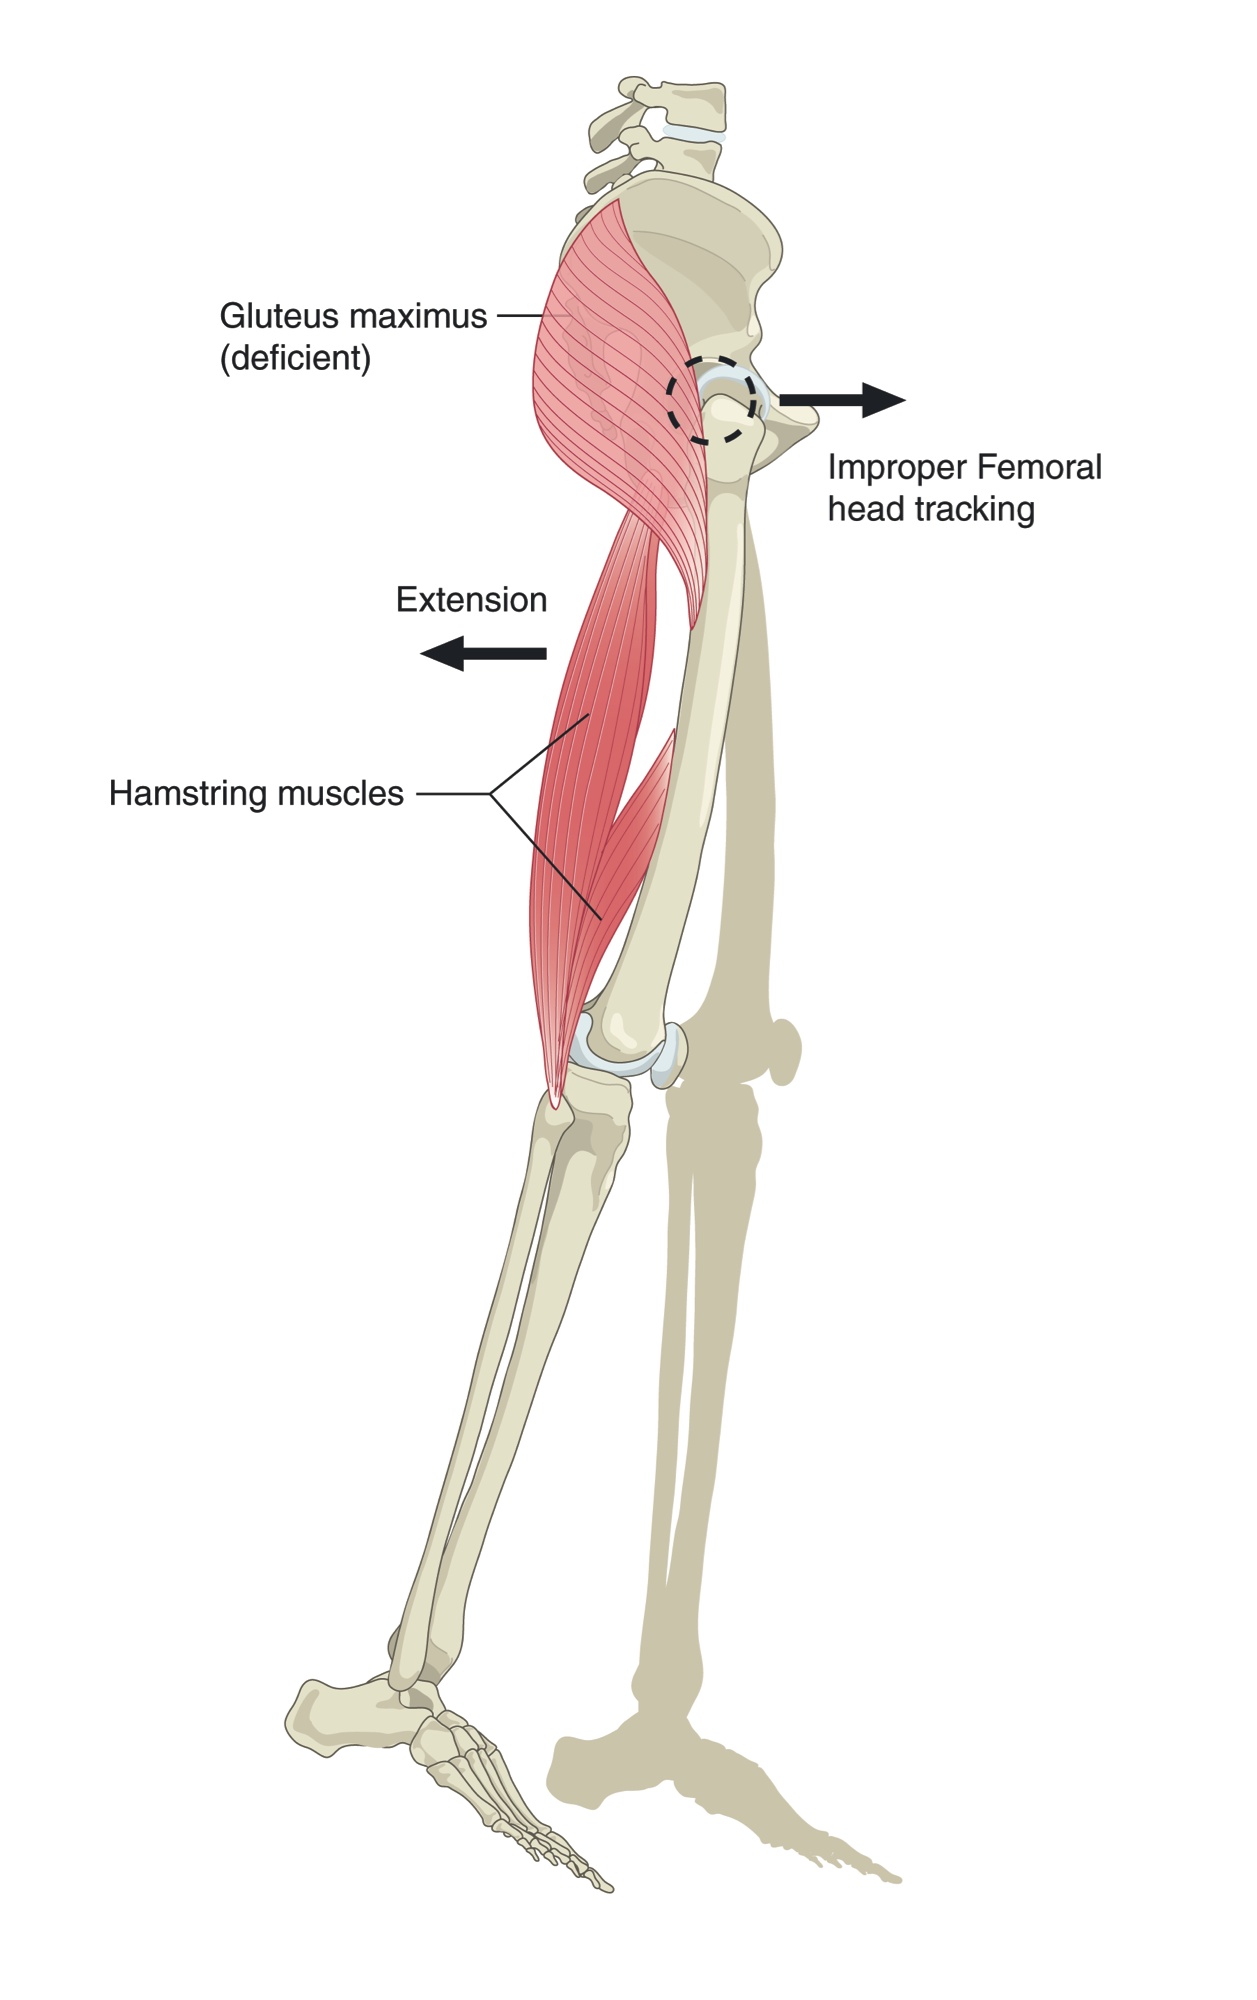
Why this causes pain. “Anterior” means forward, “femoral” means thigh bone, “glide” means sliding. When the ball of your thigh bone habitually slides forward in the socket, it changes how force gets distributed around the joint every time you take a step. Weaker or poorly timed gluteal activity directly increases that forward-directed force.3
One of the jobs of the gluteus maximus is to create a pivot point for the femur head so the hip flexes and extends smoothly, especially while walking. Classic EMG research confirms this is meant to happen on every stride.8 When the gluteals don’t work well, that pivot becomes sloppy — like a washing machine that’s out of balance, careening around in the socket doing damage.
That slide creates problems in several places at once. In front, it pinches tissue, contributing to groin pain and labral irritation. On the side, the greater trochanter rubs more than it should against the IT band and the bursa on top of it, a common driver of bursitis, linked to hip abductor weakness5 and shown to improve with targeted gluteal-loading exercise in a randomized trial.6 In back, the piriformis has to fire constantly trying to control the thigh bone to make up for the poor job the gluteus maximus is doing — leading to overuse, not tightness. This is usually what’s behind piriformis-related pain, a mechanism also described in the literature as gluteal weakness shifting load onto the piriformis.7
It doesn’t stop at the hip. Many practitioners assume hip pain is caused by the back, or that sciatica causes hip pain. In my experience it’s often the reverse: this pattern feeds a compensation pattern first, which then refers pain down the leg in the case of sciatica. I cover a dramatic example in Al’s story, where a man’s eight years of sciatica, including a failed back surgery, resolved once we addressed his hip instead of his spine. For more on the sidebending problem this pattern can create, see my sciatica article.
The real cause: glutes that aren’t firing
Quick take: A two-part self-test shows you whether your glutes are doing their job. One part checks if the muscle can contract at all; the other checks if it actually does during walking, when it matters most.
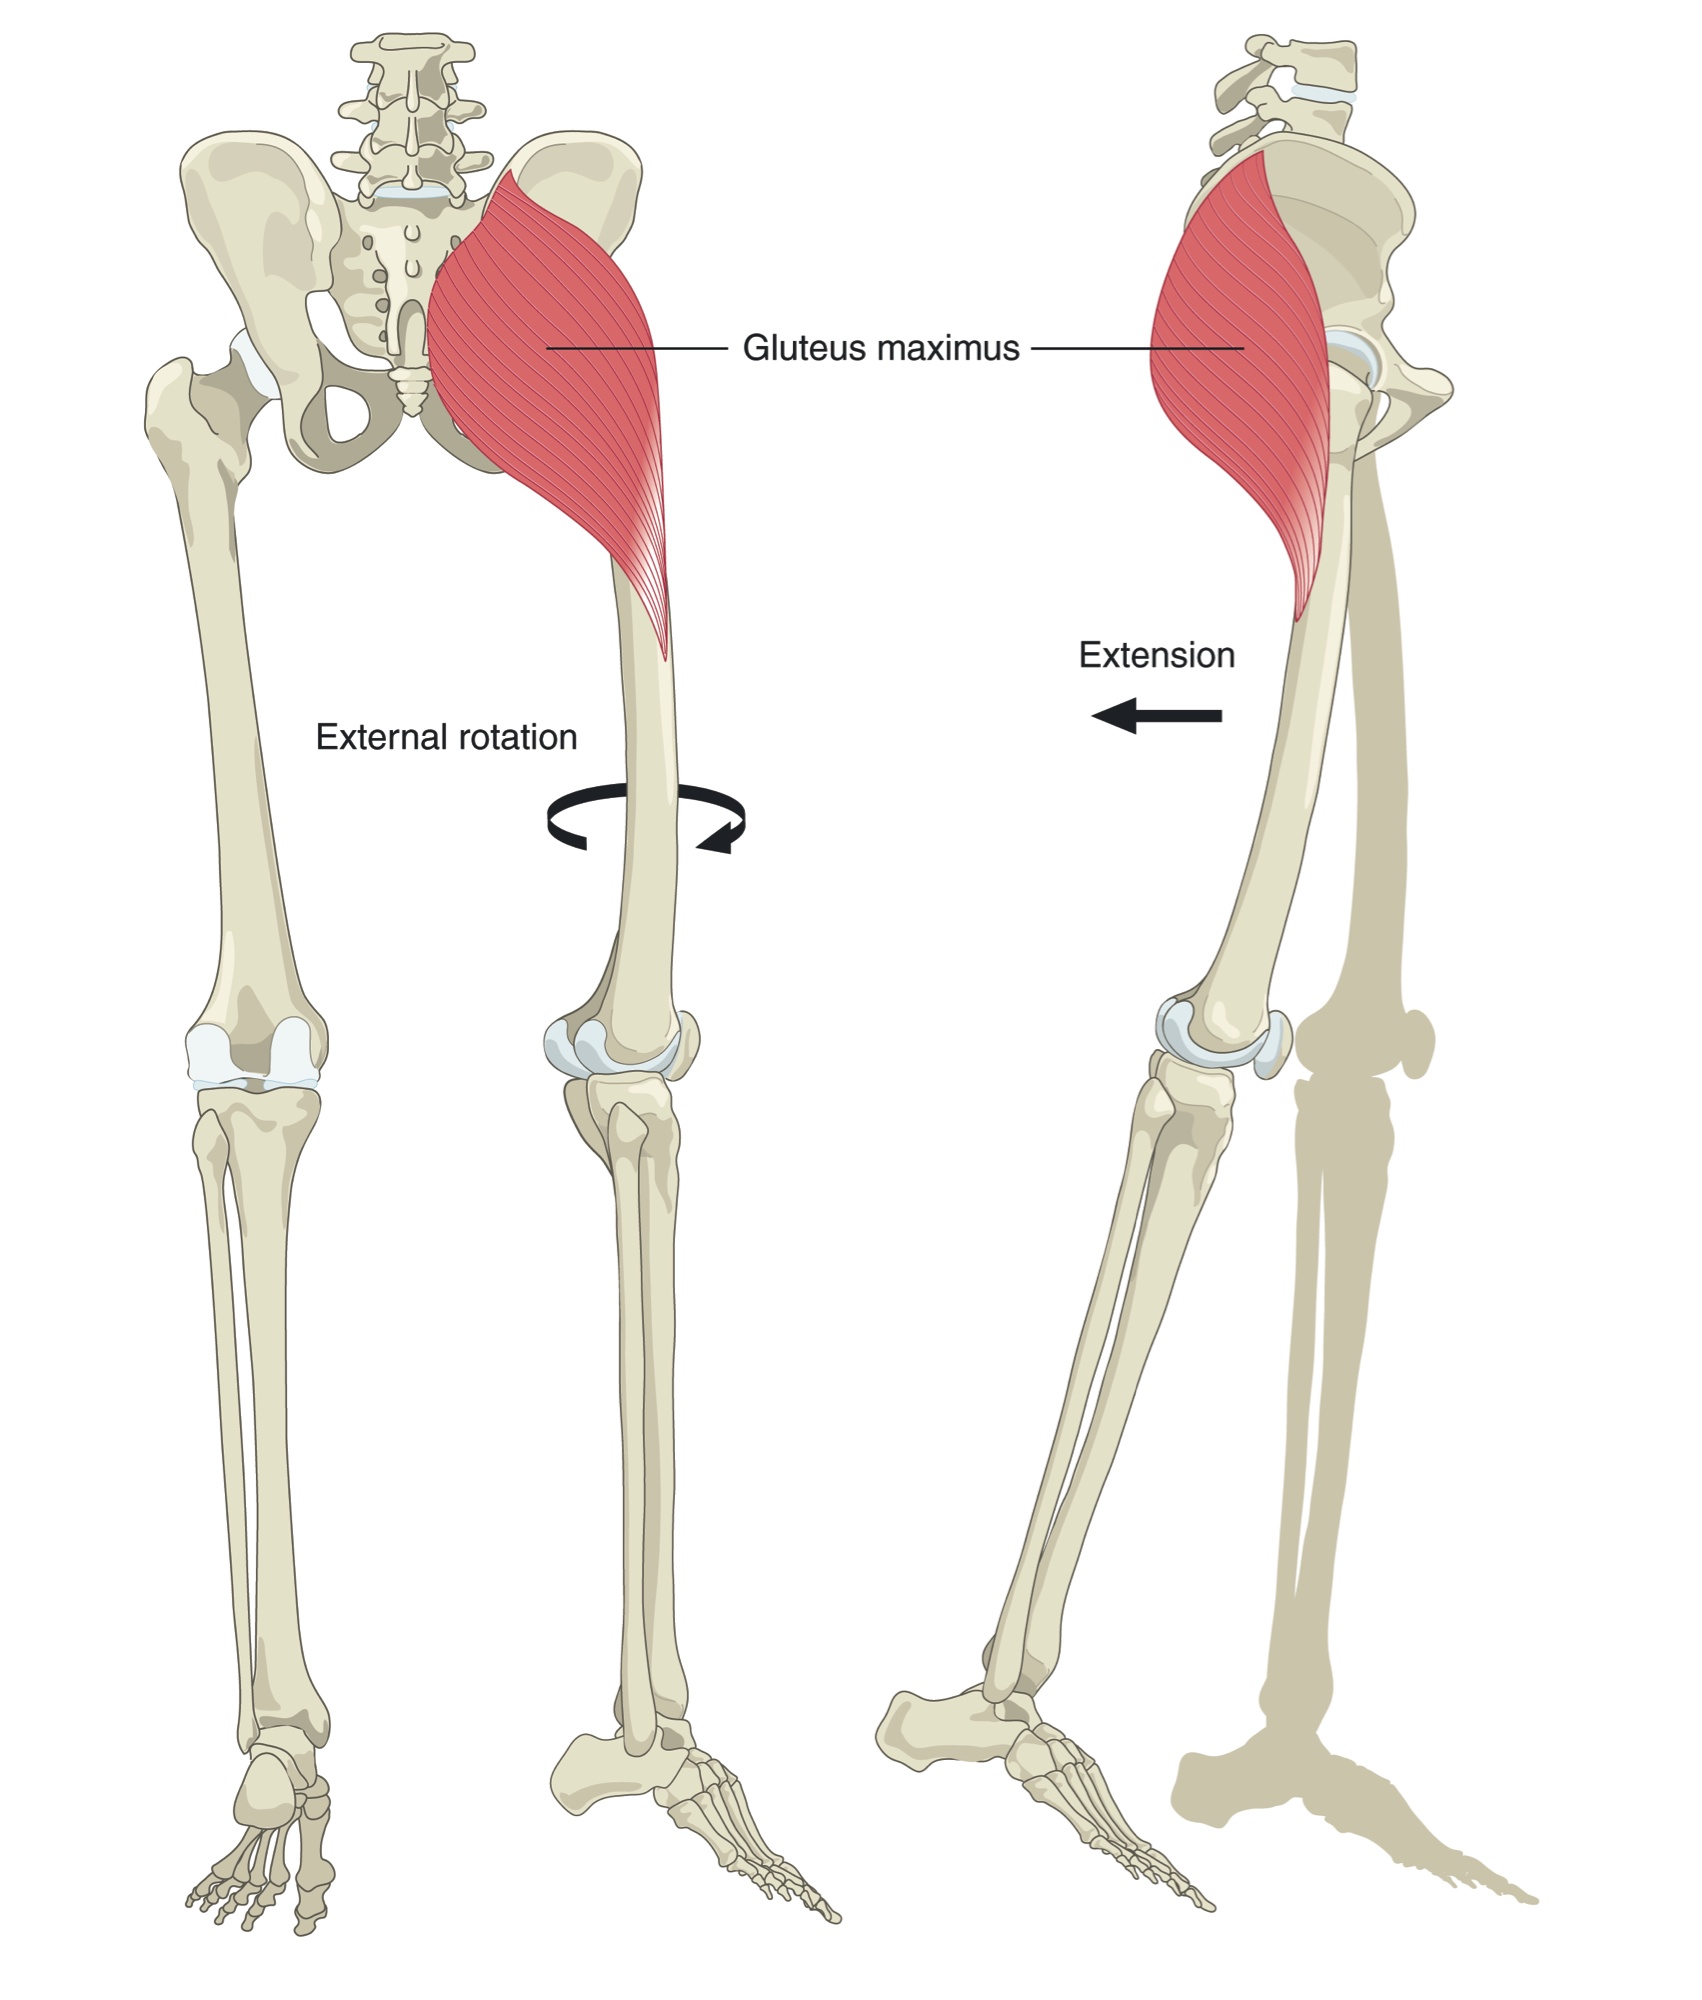
Try this test
Are your glutes working while you walk?
- Place your fingertips on the center of each butt cheek.
- Pinch your cheeks together, feel the contraction, then relax completely.
- Keeping your fingertips there, walk normally for 10 steps.
- Notice whether you feel any contraction at all while walking.

Most people with chronic hip pain feel little or nothing happening in their glutes when walking. That gap is the problem. Sylvia had the same experience.
The fix: butt pumps
Quick take: A simple exercise called the butt pump retrains your glutes to activate. This exercise position has been studied directly for glute activation.10

Try this
The butt pump
- Get on your elbows and knees, or stand and lean on a countertop.
- Lift one leg to the height where you feel your glute turn on. It doesn’t need to be very high.
- Small pumps, up and down half an inch to an inch, 20 to 30 reps.
- Don’t let the leg drop too low between pumps, or the glute shuts back off.
- Switch legs. Two sets per leg.
Form note. Don’t arch your back to get the leg higher. Go only as high as it takes to feel the glute working. Not feeling the butt turn on? Slightly rotate that knee outward to help it.
The habit that’s keeping your glutes turned off
Quick take: Your everyday walking pattern is likely what turns your glutes off. A simple habit change can retrain it in days.
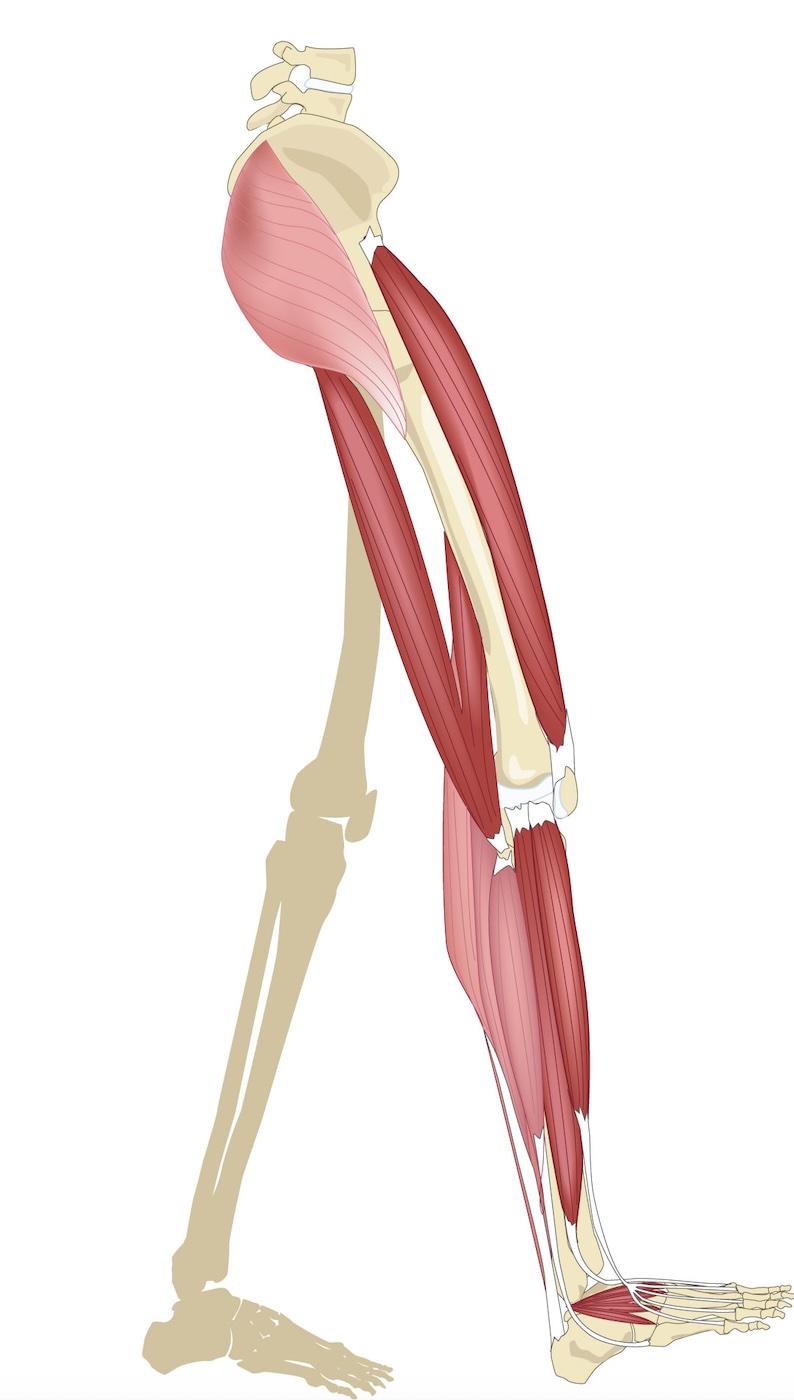
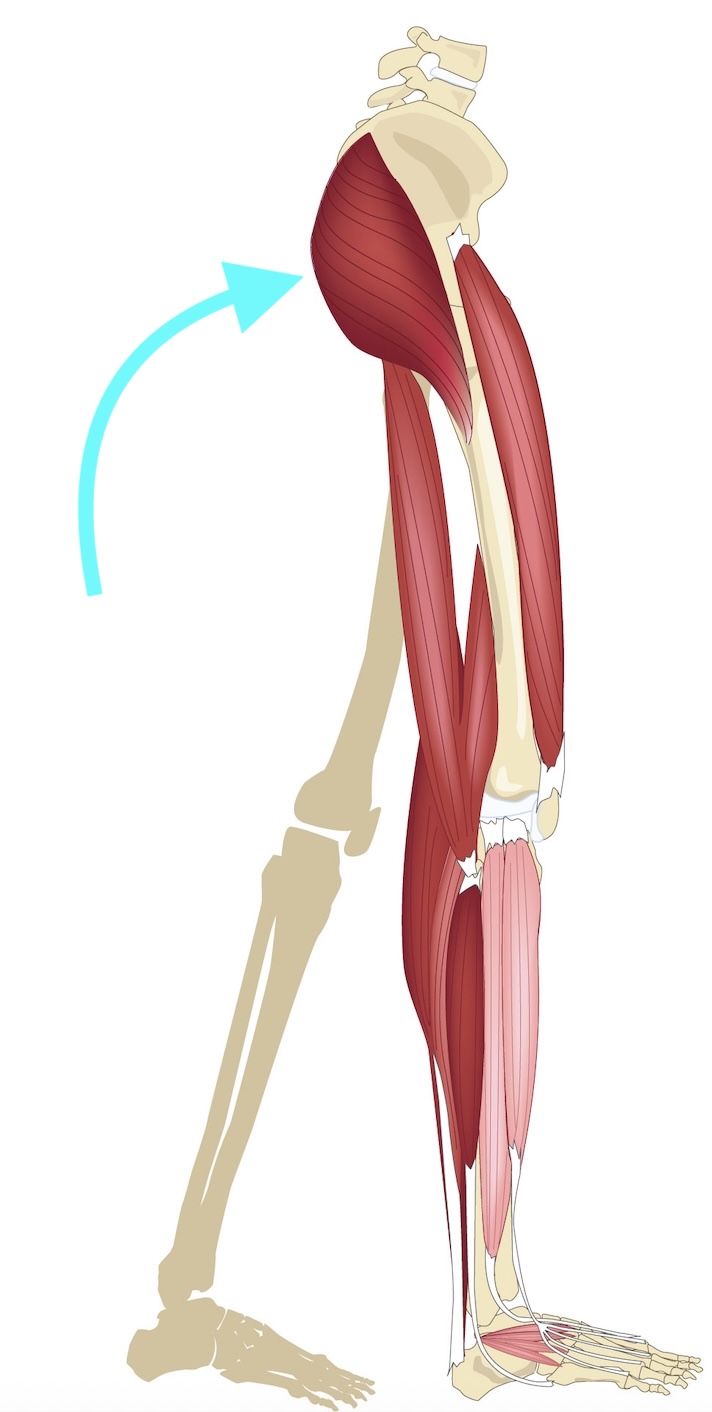
Why this causes pain. Most people walk with a strong heel strike that locks the knee. Locking the knee also pushes the hip into more extension than it needs, and walking with greater hip extension has been shown to increase the forward-directed force on the hip joint.9 In my clinical observation, that locked-knee pattern is also what shuts the glutes off.
Try this
The tiptoe cue
- Anytime you get up from a chair to walk, walk on your tiptoes for 5 to 10 steps.
- Notice your glutes turning on by checking with your fingertips.
- Slowly lower your heels and notice the contraction holding for a few more steps.
Tiptoe walking works because you can’t lock your knees while on your toes, and your body can’t lag behind your advancing foot. Repeat this cue throughout the day, every time you stand up from a chair. It’s often enough to retrain your gait pattern within days.
But I have FAI — can this still help?
Yes. Pain from FAI, or femoroacetabular impingement, typically occurs in the front of the hip in the groin area. FAI involves a buildup of bone on the femoral head (cam-type), the rim of the acetabulum (pincer-type), or both (mixed-type).12 Hip muscle weakness, including reduced glute strength, is well documented in people with symptomatic FAI.11 Instability — excessive movement of the femoral head within the socket — is also increasingly recognized as a contributing factor in FAI-related hip pain.13 Having anterior femoral glide means those surfaces come into more contact, causing pain. Improving gluteal performance helps restore the pivot point further back in the hip socket, reducing or removing that contact.
Putting it together
Groin pain, bursitis, piriformis pain, low back pain, even sciatica: in my clinical experience, these frequently trace back to the same starting point — glutes that have stopped stabilizing the hip during standing and walking, letting the thigh bone glide forward or leading to poor pelvic control. The self-test above tells you whether this is happening in your body. The butt pump rebuilds the strength piece. The tiptoe-walking habit retrains the movement pattern that turned the glutes off in the first place. It’s what changed the outcome for Sylvia.
Rick’s takeaway
An MRI can tell you what your hip looks like. It can’t tell you what your hip is doing on every step. Before you accept the scan as the whole explanation, check whether your glutes are switching on when you walk — because if they aren’t, that’s a driver you can still change.
Sylvia caught this pattern early enough that it never cost her anything beyond the hip itself. Not everyone catches it that early. One of the most common recommendations from surgeons is “come back when the pain is bad enough and we’ll do the surgery” — but what they aren’t watching for are the secondary changes that happen when people gradually begin compensating. That’s what the next article in this series covers, before the third gets to the piece hiding underneath all of it: the actual shape of your thigh bone.
Common questions
I already have significant structural damage — a torn labrum, bone-on-bone arthritis, cartilage loss. Should I just get the surgery?
Always follow your medical team’s guidance; they know the specifics of your case. That said, structural findings don’t automatically tell you what’s causing your pain, and in my experience it’s often worth spending a few weeks correcting the mechanical drivers first. I go much further into this decision, including what waiting can cost the rest of your body, in the next article in this series.
Can hip arthritis improve without hip replacement?
In many cases, yes, at least in terms of pain and function. Sylvia had worn cartilage and bone spurs and avoided surgery entirely. Improvement doesn’t mean the arthritis itself reverses — it means the mechanical stress driving the pain gets addressed, which is often enough to change the outcome.
Is anterior femoral glide syndrome a formal medical diagnosis?
It’s not a diagnosis you’ll typically hear from a doctor. It’s a movement pattern I use clinically, described in Dr. Sahrmann’s textbook Diagnosis and Treatment of Movement Impairment Syndromes, to explain and treat a range of hip-related pain.
Can this pattern cause back pain and sciatica, not just hip pain?
In my clinical experience, yes. The hip instability alters pelvic and low back mechanics, which can then impinge nerves, creating sciatica down the leg. I’ve seen this resolve sciatica that had already failed back surgery. More on this in my sciatica article.
How long does the butt pump exercise take to help?
It varies by person, but many people notice the gait-pattern habit change making a difference within one to three days, while strength changes from the exercise itself typically build over a few weeks of consistent practice.
What if I don’t feel my glutes turn on at all, even with the self-test?
That’s common, and usually just means the pattern has been present for a while. Keep practicing the fingertip check and the tiptoe cue, and activation typically starts to return with consistency. Don’t forget the butt pump exercise.
Do I need special equipment for the butt pump?
No. It’s done on the floor or a table using just your elbows and knees. As you get stronger, adding ankle weight — the way Sylvia did — can help.
Is this the same thing as femoral anteversion or retroversion?
No, though they’re related. Anterior femoral glide syndrome is about how the thigh bone moves during activity; anteversion and retroversion describe the actual twisted shape of the thigh bone itself, which I cover in the third article in this series.
Does this only affect one hip, or can both be affected?
It can affect one or both hips, depending on your individual movement pattern, strength, and history.
If your glutes weren’t switching on during the walking test
Work through the whole correction at home, in seven days
7 Days to Better Hips walks you through the tests to understand and solve the larger problems feeding your hip pain — built on the same approach I used with Sylvia, and more complete now.
Explore 7 Days to Better Hips
Prefer the full anatomy and reasoning? Fixing You: Hip & Knee Pain lays out the self-treatment approach in detail.
Some links in this article are affiliate links. If you buy through them I may earn a small commission, at no extra cost to you. I only recommend products I actually use with patients.
Have a question this article didn’t answer?
Send it through the Ask Rick form. I read every question and use the most common ones to shape future articles, videos, and my monthly email — sometimes by featuring them, never with identifying details, in a public answer. I ask for your email in case I need more detail, or want to let you know when I’ve covered it.
References
- Heerey JJ, Kemp JL, Mosler AB, et al. “What Is the Prevalence of Hip Intra-Articular Pathologies and Osteoarthritis in Active Athletes with Hip and Groin Pain Compared with Those Without? A Systematic Review and Meta-Analysis.” Sports Medicine. 2019. Found labral tears and cartilage defects at similar rates in people with hip and groin pain and in pain-free controls. ↩
- Sahrmann SA. Diagnosis and Treatment of Movement Impairment Syndromes. St. Louis, MO: Mosby; 2002. The original clinical description of anterior femoral glide syndrome as a movement-impairment pattern. ↩
- Lewis CL, Sahrmann SA, Moran DW. “Anterior Hip Joint Force Increases with Hip Extension, Decreased Gluteal Force, or Decreased Iliopsoas Force.” Journal of Biomechanics. 2007;40(16):3725–3731. ↩
- Grant C, Pajaczkowski J. “Conservative Management of Femoral Anterior Glide Syndrome: A Case Series.” Journal of the Canadian Chiropractic Association. 2018;62(3):182–192. Patients with this exact pattern achieved complete symptom resolution using conservative treatment alone. ↩
- Grimaldi A, Fearon A. “Gluteal Tendinopathy: Integrating Pathomechanics and Clinical Features in Its Management.” JOSPT. 2015;45(11):910–922. ↩
- Ganderton C, Semciw A, Cook J, Moreira E, Pizzari T. “Gluteal Loading Versus Sham Exercises to Improve Pain and Dysfunction in Postmenopausal Women with Greater Trochanteric Pain Syndrome: A Randomized Controlled Trial.” Journal of Women’s Health. 2018;27(6):815–829. ↩
- Tonley JC, et al. “Treatment of an Individual with Piriformis Syndrome Focusing on Hip Muscle Strengthening and Movement Reeducation: A Case Report.” JOSPT. 2010;40(2):103–111. ↩
- Lyons K, Perry J, Gronley JK, Barnes L, Antonelli D. “Timing and Relative Intensity of Hip Extensor and Abductor Muscle Action During Level and Stair Ambulation: An EMG Study.” Physical Therapy. 1983;63(10):1597–1605. ↩
- Lewis CL, Sahrmann SA, Moran DW. “Effect of Hip Angle on Anterior Hip Joint Force during Gait.” Gait & Posture. 2010;32(4):603–607. ↩
- Lewis CL, Sahrmann SA. “Muscle Activation and Movement Patterns During Prone Hip Extension Exercise in Women.” Journal of Athletic Training. 2009;44(3):238–248. EMG measurement of glute activation during the exact prone hip-extension position used in the butt pump. ↩
- Casartelli NC, Maffiuletti NA, Item-Glatthorn JF, et al. “Hip Muscle Weakness in Patients with Symptomatic Femoroacetabular Impingement.” Osteoarthritis and Cartilage. 2011;19(7):816–821. ↩
- Gómez-Verdejo F, Alvarado-Solorio E, Suarez-Ahedo C. “Review of Femoroacetabular Impingement Syndrome.” Journal of Hip Preservation Surgery. 2024. ↩
- Wong SE, Cogan CJ, Zhang AL. “Physical Examination of the Hip: Assessment of Femoroacetabular Impingement, Labral Pathology, and Microinstability.” Current Reviews in Musculoskeletal Medicine. 2022;15(2):38–52. ↩