Back & sciatica · Rick’s case
When sciatica isn’t about your back: 8 years of pain solved by fixing the hip
Al had a failed back surgery and eight years of sciatica. The real cause was hiding in a place no one thought to look: his hip joint.
Licensed orthopedic physical therapist with 30 years of clinical experience, former owner of an
orthopedic PT clinic, and author of the Fixing You book series, including
Fixing You: Hip & Knee Pain and the award-winning Pain Patterns
(2025 NIEA Award winner). He created an APTA-approved continuing education course teaching other
clinicians his systems-thinking approach to chronic pain.
Eight years of sciatica changed Al’s life. Not because it healed, but because every healthcare practitioner got the diagnosis wrong.
The sciatica problem wasn’t in his back at all. It was hiding in a place no one thought to look: his hip joint. And when we finally addressed the real cause — gluteal weakness and anterior femoral glide syndrome — eight years of debilitating pain vanished in 60 seconds.
This is Al’s story, and it might be yours too.
Always follow the guidance of your medical team — they know your case better than an article can. What follows isn’t a diagnosis. It’s one patient’s story and an explanation of how your body works, something to think about before you decide anything about treatment.
Al’s 8-year journey with sciatica
The 67-year-old mechanical engineer sat across from me with arms folded, his voice monotone, like Eeyore from Winnie the Pooh saying, “If it is a good morning, which I doubt.”
Eight years of sciatic pain had turned him into this. Eight years of:
- Emergency room visits for stabbing leg pain
- Failed cortisone shots
- Back surgery that helped for only six weeks
- Being told “it will heal in two to three years”
- Abandoning walks with his wife of 42 years
- Giving up yard work, his favorite pastime
- Weighing the pros and cons of a simple grocery store trip
The numbness and stabbing pains in his right leg had forced him to whittle his life down to avoid triggering episodes. He’d stopped working as a mechanical engineer. He couldn’t lift, push, or pull anything.
The failed treatments: why back-focused care didn’t work
Every medical professional reached the same conclusion: Al’s sciatic nerve was the problem, and his lower back was the source. The logic seemed sound:
- Lasegue’s Test was positive (straight leg raising reproduced his pain)
- MRI showed a disc bulge
- The pain followed the sciatic nerve distribution
So they treated his spine:
- Cortisone injections to reduce disc inflammation — failed
- Surgery to remove bone and part of a spinal disc — helped 6 weeks, then pain returned
- Physical therapy, chiropractic and other treatments focused on the lumbar spine — no lasting relief
- More tests to check for pinched nerves — all negative
After eight years, one doctor finally admitted defeat: “Whatever it is will heal over the next two to three years.” Translation: “We don’t know what’s going on.”
The 60-second fix that changed everything
I needed to do something dramatic. Al had heard it all before from a long line of healthcare professionals.
First, I confirmed what everyone else had found. I had Al lie down and perform Lasegue’s Test, raising his straight leg off the table. He could barely lift it a few inches before searing pain tore through his leg. Sweat beaded on his brow.
“That’s exactly the pain I’ve been having all these years,” he confirmed through gritted teeth.
Then I did something different. “Get onto your elbows and knees,” I instructed. He gave me a weird look. Apparently, none of the other eight years’ worth of healthcare professionals had asked this of him.
I had him lift his right leg with the knee bent and perform two sets of small pulses to activate his gluteal muscles — his butt muscles. The whole thing took maybe 60 seconds.
“Now lie on your back and lift your right leg again,” I said. He looked at me doubtfully, took a deep breath…
And his leg shot up, almost perpendicular to the ground. No pain.
He tested it ten more times. Still no pain. His Eeyore expression transformed into complete bewilderment.
“Huh? What did you do?” he asked.
“I didn’t do a thing,” I said. “You did.”
“I don’t understand, how did that fix my back?”
“It’s not your back that’s the problem. It’s your hip.”
The exercise Al did is the butt pump. See how to do it step by step.
What is anterior femoral glide syndrome?
Anterior femoral glide syndrome (AFGS) is a movement impairment where the thigh bone (femur) doesn’t glide properly in the hip socket during movement.1
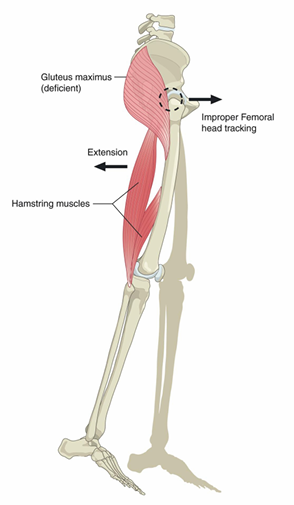
Normal hip mechanics
When you flex your hip, the rounded head of the femur should glide slightly backward (posteriorly) in the socket. This creates space and maintains proper alignment.
With AFGS
The femoral head glides forward (anteriorly) instead, causing pinching of tissues, overwork of structures in the back of the hip, irritation of the piriformis muscle, and compression of the sciatic nerve.
In Al’s case, the head of his thigh bone migrated forward when he moved his leg, causing:
- The piriformis muscle in the back of the hip to spasm
- Compression of his sciatic nerve
- Stress on his lower back from poorly controlled pelvic movement
- Eight years of debilitating pain

Watch the video versionRick Olderman on hip-related sciatica
Why gluteal weakness creates sciatica
The gluteal muscles (particularly the gluteus maximus) are primarily responsible for helping the thigh bone pivot correctly in the hip socket.
When gluteals fire properly
- The thigh bone glides correctly in the socket
- Tissues around the hip remain uncompressed
- The sciatic nerve has plenty of space
When gluteals are weak
- The femoral head slides forward uncontrolled
- The piriformis muscle compensates excessively
- The sciatic nerve gets compressed
- Pain radiates down the leg mimicking a spine problem
I could tell just by watching Al walk that his gluteals weren’t firing properly. When your butt muscles don’t activate correctly, movements get sloppy, and the sciatic nerve pays the price.
Why standard MRIs miss this diagnosis
Almost everyone has some structural anomalies in the spine, especially the older we get. Disc lesions appear on MRI in many asymptomatic people — a positive finding doesn’t mean it’s causing pain.2
What medicine often forgets: Medicine excels at identifying damaged structures. But we often forget to ask why the damage is happening. Yes, the sciatic nerve was causing Al’s pain. But the crucial question was: why was the back bothering the nerve?
The answer: poor hip mechanics from weak, poorly activated gluteal muscles.
Spine specialists typically dismiss this possibility. According to their training, if anything is wrong with the hip, it must be coming from the spine, not the other way around. This is why Al suffered so many years.
When sciatica isn’t about your back: how to tell if yours is a hip problem
If you’ve been dealing with sciatic pain that won’t respond to back-focused treatments, ask yourself these questions:
Quick self-check
Is your sciatica coming from your hip?
- Do you have back pain or just leg pain? Al never mentioned back pain — a crucial clue that his problem may not be spinal.
- Does sitting make it worse? With AFGS, the head of the femur typically glides forward the most when the hip joint is flexed or bent.
- Do spine-focused treatments fail? If surgery, spinal injections, or lumbar-focused therapy only helped temporarily, provided no relief, or made things worse — your problem may not be spinal.
- Does hip movement trigger pain? Hip-related sciatica increases with hip flexion, internal rotation, adduction, prolonged sitting, and activities requiring hip extension.
- Can you activate your glutes properly? Simple test: take 20 steps with your hands on your butt. Do you feel your butt muscles firing?
The second layer: solving Al’s lower leg numbness
A week later, Al returned. The sciatic pain was still gone. But he had a lingering issue.
“I still have numbness in my lower leg when I use it in certain ways, like moving something with my foot,” he added. I had him slide a phone book with the side of his right foot. It produced numbness. He grimaced.
Since his problem was hip-based, not spine-based, I hypothesized the lower leg numbness wasn’t coming from his back either. I used a technique called Hanna Somatics — a method that uses controlled muscle contraction and release to reduce tension and reflexive spasming. The whole process took about five minutes. (Why this works when stretching doesn’t is its own story.)
“Test your numbness now,” I said. He moved the phone book. No numbness. He moved it more, scooting it across the floor. I watched this distinguished older gentleman express pure delight at sliding a phone book with his foot. Still no numbness.
“It’s not my back,” he whispered, half to himself. “After all these years, it’s not my back.”
Why medical professionals miss hip-related sciatica
It’s not that doctors are incompetent. The diagnostic pathway is simply set up to look in the wrong place — primarily because we are trained to identify structural components of a problem, rather than systemic causes.
Standard diagnostic logic: Sciatica = sciatic nerve pain → Sciatic nerve originates in lower back → Therefore, sciatica = back problem → Order lumbar spine MRI → Treat what MRI shows.
What this misses: The sciatic nerve travels from the lower back through the deep gluteal space and down the entire leg. It can be compressed anywhere along this path.
Al’s issue likely resulted from a “slow burn” of years of sitting at work in poor posture, walking with poor technique, sleeping in a deteriorating bed, and accumulating old injuries that never fully resolved. All these tiny negatives accrued over time until pain precipitated.
Rick’s takeaway
Our movement patterns create our pain patterns.
From Eeyore to Tigger: Al’s transformation
To see eight years of frustration and pain melt away in that moment was one of the reasons I love what I do.
Al’s face showed a mixture of joy, relief, and understanding. Imagine hurting for eight years. And then, suddenly, you don’t. It can turn an Eeyore into a Tigger.
The mechanical engineer who couldn’t — now can:
- Lift, push, or pull anything
- Take walks with his wife of 42 years
- Do yard work — back to his favorite pastime
- Shop without pain calculations
— Rick’s case notes
Most importantly, he understood how his body worked and why he had pain. That knowledge meant he would never slip back into old habits.
If you’re dealing with chronic sciatica or other pain that hasn’t responded to traditional treatments, the solution may not be where you’ve been looking. Like Al, your pain might have an unexpected cause that requires a different approach.
Common questions about hip-related sciatica
Can hip problems cause sciatica?
Yes. Anterior femoral glide syndrome can cause sciatica due to compression of the sciatic nerve by non-spinal structures in the hip region. Unfortunately, most healthcare practitioners are not trained to understand AFGS. I explain how to think about these types of problems in my most recent book, Pain Patterns, available on Amazon.
What is anterior femoral glide syndrome?
Anterior femoral glide syndrome is a movement impairment where the femoral head glides forward instead of backward during hip flexion, causing tissue compression, piriformis muscle spasm, and sciatic nerve irritation. I explain AFGS in this YouTube video.
How do weak glutes cause sciatica?
Weak or poorly activated gluteal muscles fail to control the femoral head position in the hip socket. This allows the bone to migrate forward, irritating the piriformis muscle and sciatic nerve in the deep gluteal space.
Why does sitting make my sciatica worse?
Sitting compresses structures in the deep gluteal space, further irritating the sciatic nerve.
Can sciatica be cured without surgery?
Yes. If your sciatica is caused by hip dysfunction rather than severe spinal pathology, addressing gluteal weakness and hip mechanics can often resolve symptoms without surgery — sometimes in as little as 60 seconds, as in Al’s case.
How long does it take to fix hip-related sciatica?
With proper identification and treatment of the underlying hip dysfunction, many patients experience significant improvement within 1–2 weeks. Al’s acute pain resolved immediately with gluteal activation; his complete recovery took several weeks of corrective exercises.
What exercises help anterior femoral glide syndrome?
- Prone hip extension with knee bent
- Gluteal activation drills
- Hip external rotation strengthening
- Corrective movement patterns during daily activities like walking
Should I get an MRI for sciatica?
An MRI of the lumbar spine is helpful to rule out serious spinal pathology. However, a standard lumbar MRI does not visualize the deep gluteal space and cannot identify AFGS. If lumbar MRI is negative or treatments fail, consider evaluation for hip-related causes.
If this sounds like your pattern
Test and correct it at home
7 Days to a Better Back walks through the same hip and pelvis tests, with exercises matched to what you find.
Explore 7 Days to a Better Back
Want to understand pain like Al’s? Pain Patterns explains how movement patterns create pain patterns, with many more cases that reveal the often-overlooked causes of chronic pain. Use code RICKBLOG20 for 20% off my digital programs.
Some links in this article are affiliate links. If you buy through them I may earn a small commission, at no extra cost to you. This helps support my website. I only recommend products I actually use with patients.
Have a question this article didn’t answer?
Send it through the Ask Rick form. I read every question and use the most common ones to shape future articles, videos, and my monthly email — sometimes by featuring them, never with identifying details, in a public answer. I ask for your email in case I need more detail, or want to let you know when I’ve covered it.
References
- Sahrmann SA. Diagnosis and Treatment of Movement Impairment Syndromes. St. Louis, MO: Mosby; 2002. The original clinical description of anterior femoral glide syndrome as a movement-impairment pattern. Publisher page ↩
- Brinjikji W, Luetmer PH, Comstock B, et al. “Systematic Literature Review of Imaging Features of Spinal Degeneration in Asymptomatic Populations.” American Journal of Neuroradiology. 2015;36(4):811–816. Disc bulges and degeneration are common on imaging in people with no back pain, and become more common with age. PubMed ↩